外科学 · O/13
胆道腫瘍(胆管癌・胆嚢癌)
Tumors of the biliary tract (bile duct and gallbladder)
🧠 胆道腫瘍biliary tract tumor 胆道腫瘍(biliary tract tumor)biliary tract tumor(胆道腫瘍) は「どの高さの胆管から出たか」で術式が変わる腺癌。 肝内intrahepatic 肝内(intrahepatic)intrahepatic(肝内) なら肝切除 hepatectomy (liver resection)肝切除(hepatectomy (liver resection)) hepatectomy (liver resection)(肝切除)、肝門部なら進展範囲に応じた肝切除 hepatectomy (liver resection) 肝切除(hepatectomy (liver resection)) hepatectomy (liver resection)(肝切除) +胆管切除1、遠位なら膵頭十二指腸切除 pancreaticoduodenectomy 膵頭十二指腸切除(pancreaticoduodenectomy) pancreaticoduodenectomy(膵頭十二指腸切除) を行い、いずれもR0切除 R0 resection R0切除(R0 resection) R0 resection(R0切除) を目指す。胆嚢癌gallbladder cancer 胆嚢癌(gallbladder cancer)gallbladder cancer(胆嚢癌) は無症候または胆石・胆嚢炎様症状で見つかり、新規診断の半数超は良性と思って行った腹腔鏡下胆嚢摘出術 laparoscopic cholecystectomy 腹腔鏡下胆嚢摘出術(laparoscopic cholecystectomy) laparoscopic cholecystectomy(腹腔鏡下胆嚢摘出術) のあとの偶発診断である。2 詳細は胆道癌biliary tract cancer胆道癌(biliary tract cancer)biliary tract cancer(胆道癌)のノートも参照。
1. 胆管癌
- 腺癌、好発年齢60〜70歳、男性に多い
- 胆管由来で、解剖学的な発生部位によって分類される
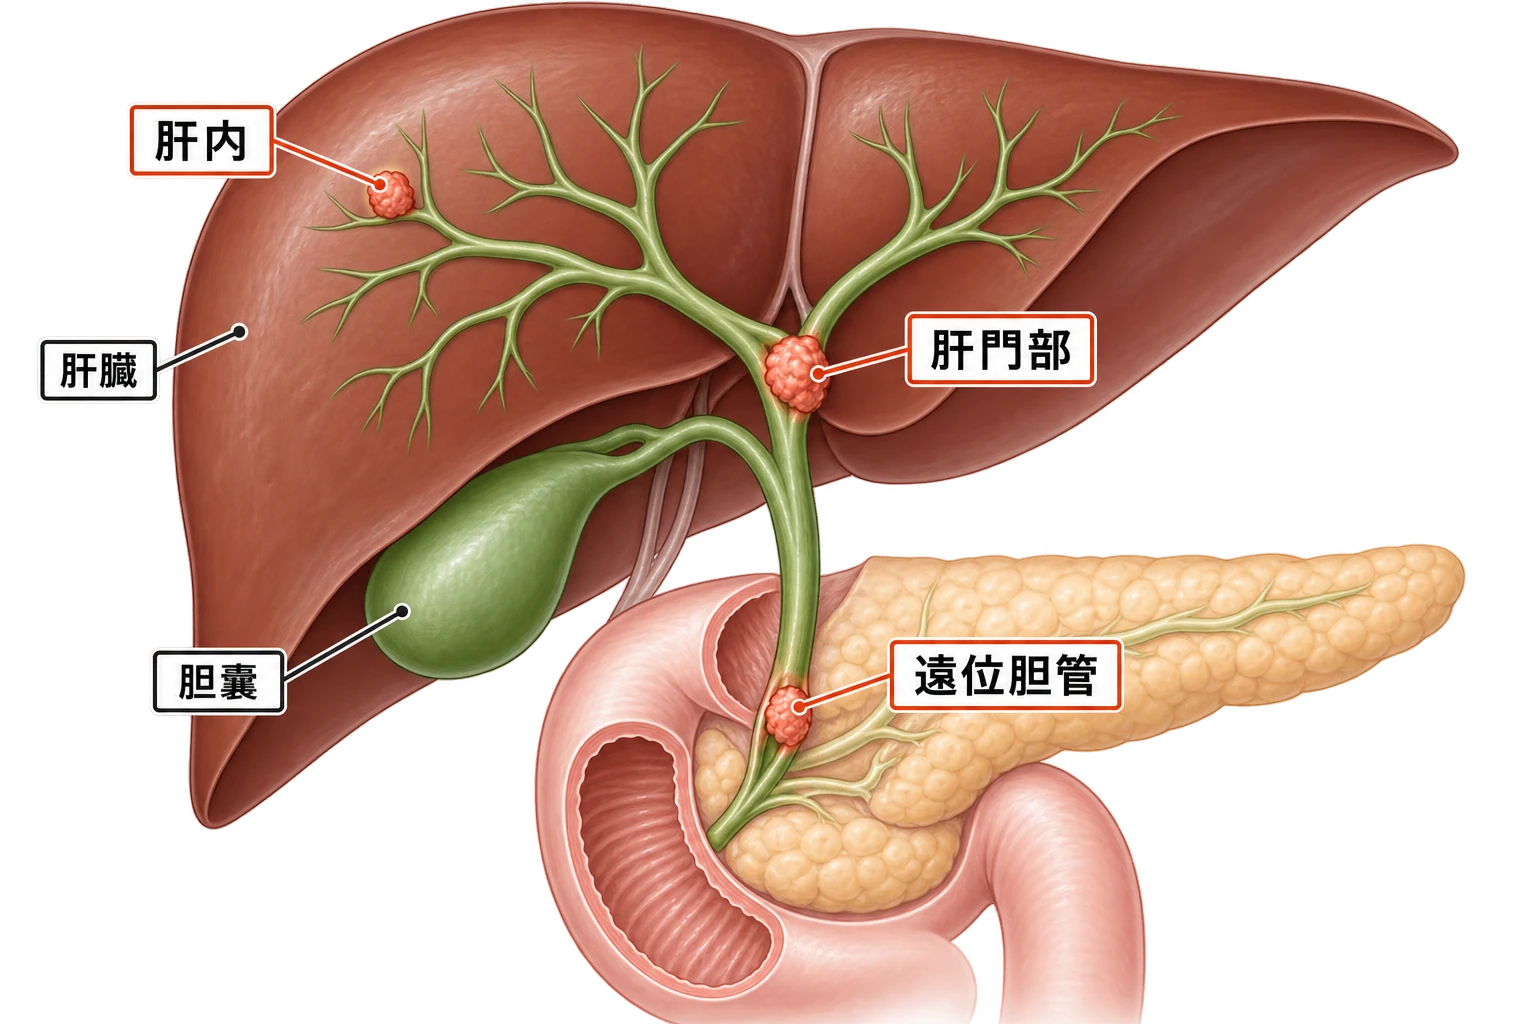
生成模式図(実際の患者画像ではありません)。
flowchart TD
  CC["<span class='jp-term jp-term-diagram' title='cholangiocarcinoma'>胆管癌</span>"]
  CC --> IH["<span class='jp-term jp-term-diagram' title='intrahepatic cholangiocarcinoma, ICC'>肝内胆管癌</span><br>(小〜中型胆管由来)<br>→ <span class='jp-term jp-term-diagram' title='hepatectomy (liver resection)'>肝切除</span>+リンパ節評価"]
  CC --> EH["<span class='jp-term jp-term-diagram' title='extrahepatic cholangiocarcinoma'>肝外胆管癌</span><br>(大型胆管由来・より多い)"]
  EH --> DI["<span class='jp-term jp-term-diagram' title='distal cholangiocarcinoma'>遠位胆管癌</span><br>(<span class='jp-term jp-term-diagram' title='common bile duct (CBD)'>総胆管</span>・膵内胆管)<br>→ <span class='jp-term jp-term-diagram' title='pancreaticoduodenectomy'>膵頭十二指腸切除</span>でR0を目指す"]
  EH --> PH["<span class='jp-term jp-term-diagram' title='perihilar cholangiocarcinoma'>肝門部胆管癌</span>(<span class='jp-term jp-term-diagram' title='Klatskin tumor'>Klatskin腫瘍</span>)<br>(肝管分岐部)<br>→ 進展範囲に応じた<span class='jp-term jp-term-diagram' title='hepatectomy (liver resection)'>肝切除</span>+胆管切除"]
部位分類:
- 肝内intrahepatic肝内(intrahepatic)intrahepatic(肝内) → 小〜中型胆管由来
- 肝外extrahepatic肝外(extrahepatic)extrahepatic(肝外) → 大型胆管由来(より頻度が高い)
- 遠位型distal遠位型(distal)distal(遠位型): 総胆管common bile duct (CBD) 総胆管(common bile duct (CBD))common bile duct (CBD)(総胆管) に発生し、根治切除curative resection 根治切除(curative resection)curative resection(根治切除) 可能例では膵頭十二指腸切除術 pancreaticoduodenectomy 膵頭十二指腸切除術(pancreaticoduodenectomy) pancreaticoduodenectomy(膵頭十二指腸切除術) を行ってR0切除 R0 resection R0切除(R0 resection) R0 resection(R0切除) を目指す
- 肝門部型perihilar (hilar) type 肝門部型(perihilar (hilar) type)perihilar (hilar) type(肝門部型) (Klatskin腫瘍Klatskin tumorKlatskin腫瘍(Klatskin tumor)Klatskin tumor(Klatskin腫瘍)): 二次分枝胆管second-order bile duct 二次分枝胆管(second-order bile duct)second-order bile duct(二次分枝胆管) と胆嚢管 cystic duct 胆嚢管(cystic duct) cystic duct(胆嚢管) 合流部 confluence (duct junction) 合流部(confluence (duct junction)) confluence (duct junction)(合流部) のあいだに発生し、胆管癌cholangiocarcinoma 胆管癌(cholangiocarcinoma)cholangiocarcinoma(胆管癌) 全体の50〜60%を占める。標準術式は拡大右肝切除extended right hepatectomy 拡大右肝切除(extended right hepatectomy)extended right hepatectomy(拡大右肝切除) または左肝切除 left hepatectomy 左肝切除(left hepatectomy) left hepatectomy(左肝切除) に、胆管切除・肝門部リンパ節郭清hepatic hilar lymph node dissection肝門部リンパ節郭清(hepatic hilar lymph node dissection)hepatic hilar lymph node dissection(肝門部リンパ節郭清)・胆道再建biliary reconstruction 胆道再建(biliary reconstruction)biliary reconstruction(胆道再建) を加えたもので、どちら側を切除するかは腫瘍の進展方向・血管浸潤vascular invasion血管浸潤(vascular invasion)vascular invasion(血管浸潤)・将来肝残量から個別に決める1。⚠️ 講義スライド slide スライド(slide) slide(スライド) は「拡大左肝切除extended left hepatectomy拡大左肝切除(extended left hepatectomy)extended left hepatectomy(拡大左肝切除)」と一律に書いているが、切除側は固定されない
⭐ 尾状葉切除caudate lobectomy 尾状葉切除(caudate lobectomy)caudate lobectomy(尾状葉切除) を忘れない。 尾状葉caudate lobe 尾状葉(caudate lobe)caudate lobe(尾状葉) を追加切除すると断端陰性切除の頻度と生存が改善し、合併症の有意な増加は伴わないとされる。1
Bismuth-Corlette分類Bismuth-Corlette classificationBismuth-Corlette分類(Bismuth-Corlette classification)Bismuth-Corlette classification(Bismuth-Corlette分類)(肝門部型perihilar (hilar) type 肝門部型(perihilar (hilar) type)perihilar (hilar) type(肝門部型) の胆管浸潤の広がりによる分類):
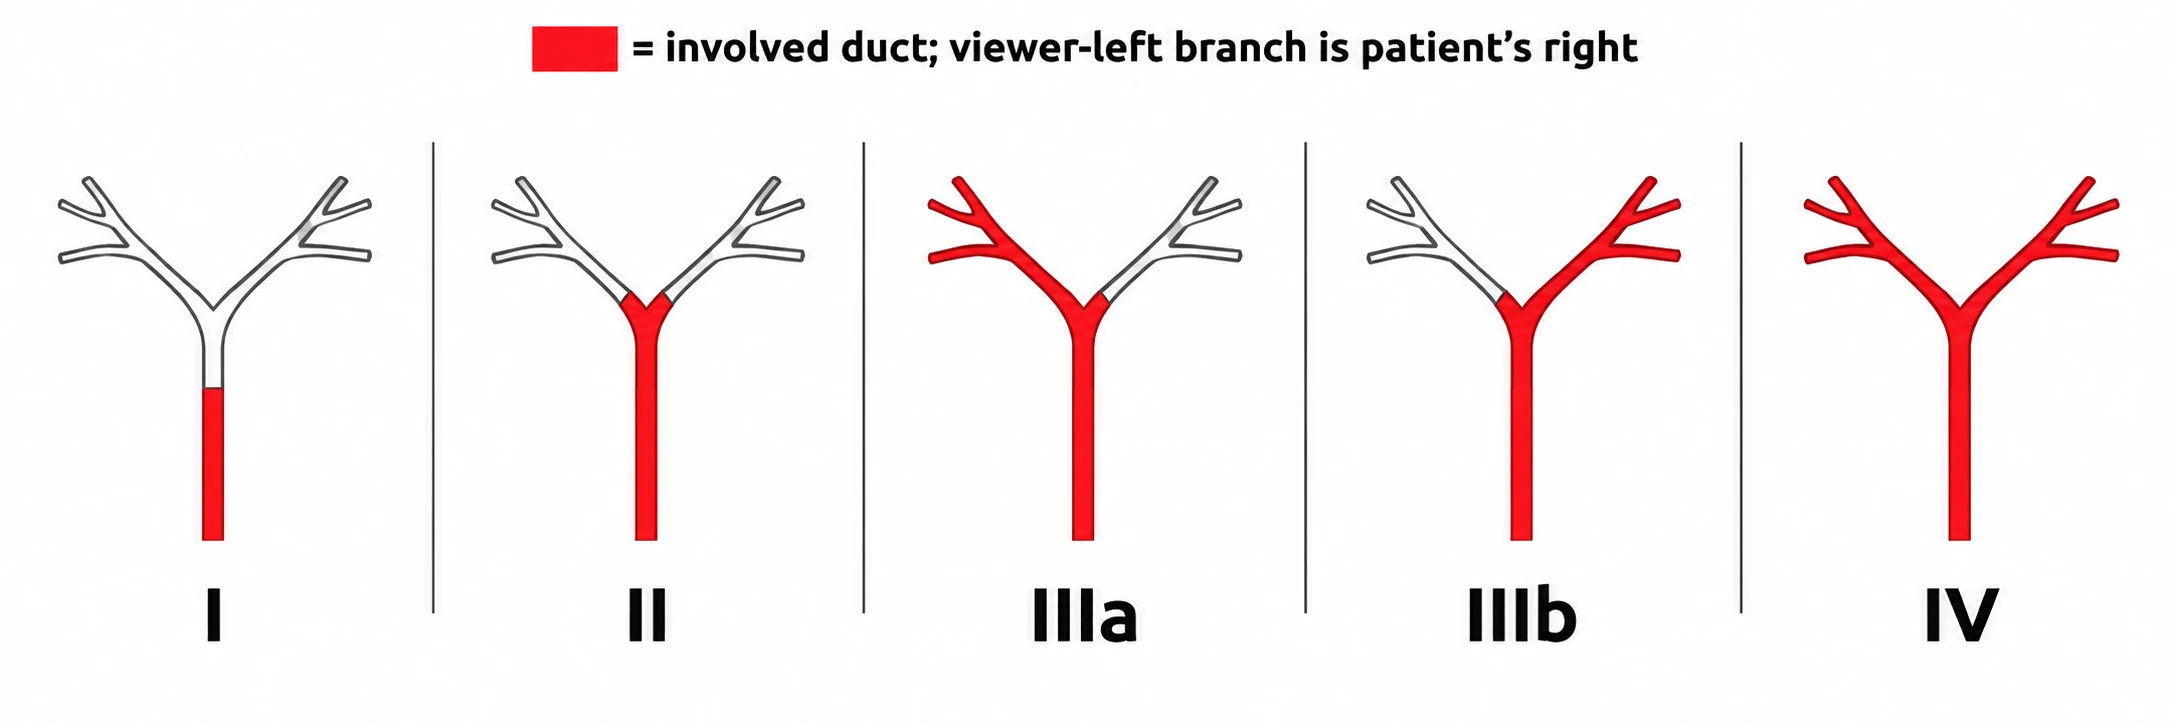
生成模式図(実際の患者画像ではありません)。
| 型 | 浸潤範囲 |
|---|---|
| I | 右肝管right hepatic duct右肝管(right hepatic duct)right hepatic duct(右肝管)・左肝管left hepatic duct 左肝管(left hepatic duct)left hepatic duct(左肝管) の分岐部より下 |
| II | 分岐部に及ぶ |
| III (a/b) | 右または左いずれかの肝管に及ぶ(a=右、b=左) |
| IV | 左右両側の二次分枝胆管 second-order bile duct 二次分枝胆管(second-order bile duct) second-order bile duct(二次分枝胆管) まで及ぶ(または多中心性)。講義スライド slide スライド(slide) slide(スライド) の図は「総肝管common hepatic duct 総肝管(common hepatic duct)common hepatic duct(総肝管) +右肝管 right hepatic duct 右肝管(right hepatic duct) right hepatic duct(右肝管) +左肝管 left hepatic duct左肝管(left hepatic duct) left hepatic duct(左肝管)」という書き方をしているが、いずれも分岐部を越えて両側へ進展した病変を指している |
⚠️ Bismuth-Corlette分類Bismuth-Corlette classification Bismuth-Corlette分類(Bismuth-Corlette classification)Bismuth-Corlette classification(Bismuth-Corlette分類) は胆管への進展を整理する分類であって、切除可能性resectability 切除可能性(resectability)resectability(切除可能性) を予測しない(AJCC病期分類 staging 病期分類(staging) staging(病期分類) も同様)。切除の可否は、経験ある放射線科医 radiologist放射線科医(radiologist) radiologist(放射線科医)・腫瘍内科medical oncology 腫瘍内科(medical oncology)medical oncology(腫瘍内科) 医・外科医が参加する多職種カンファレンスで決めるべきとされる。後腹膜・腹腔動脈celiac trunk 腹腔動脈(celiac trunk)celiac trunk(腹腔動脈) 周囲のリンパ節転移、肝外extrahepatic 肝外(extrahepatic)extrahepatic(肝外) 隣接臓器浸潤 organ infiltration臓器浸潤(organ infiltration) organ infiltration(臓器浸潤)、播種はいずれも根治手術 curative surgery 根治手術(curative surgery) curative surgery(根治手術) の相対的または絶対的禁忌 absolute contraindication 絶対的禁忌(absolute contraindication) absolute contraindication(絶対的禁忌) とされてきた。1
危険因子:
- 原発性硬化性胆管炎primary sclerosing cholangitis原発性硬化性胆管炎(primary sclerosing cholangitis)primary sclerosing cholangitis(原発性硬化性胆管炎)、胆管結石症Choledocholithiasis胆管結石症(Choledocholithiasis)Choledocholithiasis(胆管結石症)・肝内結石症hepatolithiasis肝内結石症(hepatolithiasis)hepatolithiasis(肝内結石症)
- 肝硬変、慢性ウイルス性肝炎viral hepatitisウイルス性肝炎(viral hepatitis)viral hepatitis(ウイルス性肝炎)
- 先天性の胆道拡張(総胆管嚢胞choledochal cyst総胆管嚢胞(choledochal cyst)choledochal cyst(総胆管嚢胞)、Caroli病Caroli diseaseCaroli病(Caroli disease)Caroli disease(Caroli病))や肝吸虫 liver fluke 肝吸虫(liver fluke) liver fluke(肝吸虫) 感染(流行地域endemic region流行地域(endemic region)endemic region(流行地域))3
⚠️ 講義スライド slide スライド(slide) slide(スライド) にある「ポリープ・腺腫・乳頭腫は前癌」と一括りにした整理は正確でない。胆管腺腫bile duct adenoma 胆管腺腫(bile duct adenoma)bile duct adenoma(胆管腺腫) などの良性病変と、胆管内乳頭状腫瘍intraductal papillary neoplasm of the bile duct 胆管内乳頭状腫瘍(intraductal papillary neoplasm of the bile duct)intraductal papillary neoplasm of the bile duct(胆管内乳頭状腫瘍) などの前癌病変 precancerous lesion 前癌病変(precancerous lesion) precancerous lesion(前癌病変) は病理学的に区別される。胆管内乳頭状腫瘍intraductal papillary neoplasm of the bile duct 胆管内乳頭状腫瘍(intraductal papillary neoplasm of the bile duct)intraductal papillary neoplasm of the bile duct(胆管内乳頭状腫瘍) は浸潤癌を伴うことがあるが、一般的な胆嚢ポリープ gallbladder polyp 胆嚢ポリープ(gallbladder polyp) gallbladder polyp(胆嚢ポリープ) 全てと同義ではない。先天性総胆管嚢胞congenital choledochal cyst 先天性総胆管嚢胞(congenital choledochal cyst)congenital choledochal cyst(先天性総胆管嚢胞) やCaroli病 Caroli disease Caroli病(Caroli disease) Caroli disease(Caroli病) も腫瘍ではなく、胆管癌cholangiocarcinoma 胆管癌(cholangiocarcinoma)cholangiocarcinoma(胆管癌) リスクが上昇する先天性胆道疾患 biliary disease 胆道疾患(biliary disease) biliary disease(胆道疾患) である3
臨床像:
肝外胆管癌extrahepatic cholangiocarcinoma肝外胆管癌(extrahepatic cholangiocarcinoma)extrahepatic cholangiocarcinoma(肝外胆管癌):
- 胆汁うっ滞の徴候(進行性無痛性黄疸 painless jaundice無痛性黄疸(painless jaundice) painless jaundice(無痛性黄疸)、褐色尿dark urine褐色尿(dark urine)dark urine(褐色尿)、灰白色便acholic stool灰白色便(acholic stool)acholic stool(灰白色便)、掻痒)
- 腹痛、発熱(感染を伴えば胆管炎)、食欲不振anorexia食欲不振(anorexia)anorexia(食欲不振)、体重減少
- Courvoisier徴候Courvoisier signCourvoisier徴候(Courvoisier sign)Courvoisier sign(Courvoisier徴候) → 無痛性・非圧痛性に触知できる腫大胆嚢
肝内胆管癌intrahepatic cholangiocarcinoma, ICC肝内胆管癌(intrahepatic cholangiocarcinoma, ICC)intrahepatic cholangiocarcinoma, ICC(肝内胆管癌):
- 鈍い右季肋部痛 right upper quadrant pain (RUQ pain) 右季肋部痛(right upper quadrant pain (RUQ pain)) right upper quadrant pain (RUQ pain)(右季肋部痛) または心窩部痛 epigastric pain心窩部痛(epigastric pain) epigastric pain(心窩部痛)
- 非特異的症状(体重減少、悪心、発熱、倦怠感)
診断:
| 検査 | ポイント |
|---|---|
| 血液検査 | 肝トランスアミナーゼhepatic transaminases (ALT/AST) 肝トランスアミナーゼ(hepatic transaminases (ALT/AST))hepatic transaminases (ALT/AST)(肝トランスアミナーゼ) ↑、腫瘍マーカーtumor markers 腫瘍マーカー(tumor markers)tumor markers(腫瘍マーカー) (CA19-9、CEA)↑。⚠️ どちらも胆管癌 cholangiocarcinoma 胆管癌(cholangiocarcinoma) cholangiocarcinoma(胆管癌) に特異的ではなく予後情報にとどまる。とくにCA19-9は高ビリルビン血症 Hyperbilirubinemia 高ビリルビン血症(Hyperbilirubinemia) Hyperbilirubinemia(高ビリルビン血症) で偽高値 falsely elevated (value)偽高値(falsely elevated (value)) falsely elevated (value)(偽高値)になるので、閉塞性黄疸obstructive jaundice閉塞性黄疸(obstructive jaundice)obstructive jaundice(閉塞性黄疸)・胆道感染の改善後に解釈する1 |
| 経腹壁transabdominal 経腹壁(transabdominal)transabdominal(経腹壁) US | 胆道拡張や閉塞レベル、胆嚢病変のスクリーニングに有用。講義スライド slide スライド(slide) slide(スライド) は用途として閉塞部位の同定、胆嚢・胆管拡張bile duct dilatation 胆管拡張(bile duct dilatation)bile duct dilatation(胆管拡張) の確認、局所転移の同定、US下生検を挙げている |
| 造影CT・MRI/MRCP | 胆管内進展、血管浸潤vascular invasion血管浸潤(vascular invasion)vascular invasion(血管浸潤)、肝萎縮、リンパ節・遠隔転移、将来残肝future liver remnant (FLR) 将来残肝(future liver remnant (FLR))future liver remnant (FLR)(将来残肝) 容量を評価する。将来残肝future liver remnant (FLR) 将来残肝(future liver remnant (FLR))future liver remnant (FLR)(将来残肝) 容量が不十分なら大量肝切除 hepatectomy (liver resection) 肝切除(hepatectomy (liver resection)) hepatectomy (liver resection)(肝切除) の前に門脈塞栓術portal vein embolization門脈塞栓術(portal vein embolization)portal vein embolization(門脈塞栓術)を検討する(40論文・2,144例の系統的レビューでは門脈塞栓術 portal vein embolization 門脈塞栓術(portal vein embolization) portal vein embolization(門脈塞栓術) 後の肝切除 hepatectomy (liver resection) 肝切除(hepatectomy (liver resection)) hepatectomy (liver resection)(肝切除) 率は肝細胞癌 hepatocellular carcinoma, HCC 肝細胞癌(hepatocellular carcinoma, HCC) hepatocellular carcinoma, HCC(肝細胞癌) 90%、肝門部胆管癌perihilar cholangiocarcinoma 肝門部胆管癌(perihilar cholangiocarcinoma)perihilar cholangiocarcinoma(肝門部胆管癌) 86%だった)4。MRCPは直接胆道造影 cholangiogram 胆道造影(cholangiogram) cholangiogram(胆道造影) (ERCP)より病期診断 staging 病期診断(staging) staging(病期診断) の感度・特異度・精度が高い可能性があり、胆道ドレナージbiliary drainage 胆道ドレナージ(biliary drainage)biliary drainage(胆道ドレナージ) やステント留置 stenting ステント留置(stenting) stenting(ステント留置) の前に撮るのが望ましい(アーチファクトartifact アーチファクト(artifact)artifact(アーチファクト) で読めなくなるため)1 |
| ERCP・経皮経肝胆道造影percutaneous transhepatic cholangiography経皮経肝胆道造影(percutaneous transhepatic cholangiography)percutaneous transhepatic cholangiography(経皮経肝胆道造影) | 胆管ブラッシングbile duct brushing胆管ブラッシング(bile duct brushing)bile duct brushing(胆管ブラッシング)・生検と胆道ドレナージ biliary drainage 胆道ドレナージ(biliary drainage) biliary drainage(胆道ドレナージ) が必要な場合に行う(診断のみには必須でない)。肝門部胆管癌perihilar cholangiocarcinoma 肝門部胆管癌(perihilar cholangiocarcinoma)perihilar cholangiocarcinoma(肝門部胆管癌) が疑われ大量肝切除 hepatectomy (liver resection) 肝切除(hepatectomy (liver resection)) hepatectomy (liver resection)(肝切除) を要した症例の後ろ向き解析 retrospective analysis 後ろ向き解析(retrospective analysis) retrospective analysis(後ろ向き解析) では、術前内視鏡的ドレナージ群は経皮経肝ドレナージ群より感染性合併症 septic complications 感染性合併症(septic complications) septic complications(感染性合併症) が有意に多く(48%対9%)、手技選択にはいずれにも一長一短があり施設方針と個々の解剖で選ぶ5 |
| 胆道鏡cholangioscopy胆道鏡(cholangioscopy)cholangioscopy(胆道鏡) | 標準的な胆管ブラッシング bile duct brushing胆管ブラッシング(bile duct brushing) bile duct brushing(胆管ブラッシング)・生検で確定しない狭窄の選択例で、胆管内を直視しながら標的生検 targeted biopsy 標的生検(targeted biopsy) targeted biopsy(標的生検) を追加する。全例に行う検査ではなく、専門性と利用可能性を踏まえて選ぶ6 |
| PET-CT | 他検査で判断困難な場合の病期診断 staging病期診断(staging) staging(病期診断)。CT単独より所属リンパ節・遠隔転移の検出精度が高く、約25%で方針が変わりうる1 |
治療:
- 外科的切除が唯一の根治的治療 curative therapy根治的治療(curative therapy) curative therapy(根治的治療) → 5年生存率10〜30%
- 肝内胆管癌intrahepatic cholangiocarcinoma, ICC肝内胆管癌(intrahepatic cholangiocarcinoma, ICC)intrahepatic cholangiocarcinoma, ICC(肝内胆管癌) → 部分(肝)切除+リンパ節評価
- 肝外胆管癌extrahepatic cholangiocarcinoma肝外胆管癌(extrahepatic cholangiocarcinoma)extrahepatic cholangiocarcinoma(肝外胆管癌) → 完全切除+領域リンパ節 regional lymph node 領域リンパ節(regional lymph node) regional lymph node(領域リンパ節) 郭清。なお早期の切除不能 unresectable 切除不能(unresectable) unresectable(切除不能) 肝門部胆管癌 perihilar cholangiocarcinoma 肝門部胆管癌(perihilar cholangiocarcinoma) perihilar cholangiocarcinoma(肝門部胆管癌) の一部は、厳格な選択基準・術前治療neoadjuvant therapy術前治療(neoadjuvant therapy)neoadjuvant therapy(術前治療)・病期診断staging 病期診断(staging)staging(病期診断) を含む専門施設プロトコル下で肝移植liver transplantation肝移植(liver transplantation)liver transplantation(肝移植)の対象となる(一般的な胆管癌 cholangiocarcinoma 胆管癌(cholangiocarcinoma) cholangiocarcinoma(胆管癌) すべてに肝移植 liver transplantation 肝移植(liver transplantation) liver transplantation(肝移植) を適用しない)
- 術後補助療法postoperative adjuvant therapy 術後補助療法(postoperative adjuvant therapy)postoperative adjuvant therapy(術後補助療法) としてカペシタビンcapecitabineカペシタビン(capecitabine)capecitabine(カペシタビン)が推奨される(ESMO:[II, A])7
- 切除不能unresectable切除不能(unresectable)unresectable(切除不能)・転移性 → 一次全身療法 systemic therapy 全身療法(systemic therapy) systemic therapy(全身療法) はゲムシタビンgemcitabineゲムシタビン(gemcitabine)gemcitabine(ゲムシタビン)+シスプラチンが標準(ESMO:PS 0-1で[I, A])で、これに免疫チェックポイント阻害薬 immune checkpoint inhibitor (ICI) 免疫チェックポイント阻害薬(immune checkpoint inhibitor (ICI)) immune checkpoint inhibitor (ICI)(免疫チェックポイント阻害薬) を加える。ESMOの2025年中間更新はデュルバルマブdurvalumabデュルバルマブ(durvalumab)durvalumab(デュルバルマブ)併用とペムブロリズマブpembrolizumabペムブロリズマブ(pembrolizumab)pembrolizumab(ペムブロリズマブ)併用の両方を一次治療として推奨し([I, A])、2剤を選び分ける臨床的・生化学的・分子的な指標は無く、有効性・毒性にも特筆すべき差は無いと明記する8。デュルバルマブdurvalumab デュルバルマブ(durvalumab)durvalumab(デュルバルマブ) の根拠である第3相TOPAZ-1試験(未治療685例)では、全生存overall survival (OS) 全生存(overall survival (OS))overall survival (OS)(全生存) が改善し(初回解析ハザード比 hazard ratio ハザード比(hazard ratio) hazard ratio(ハザード比) 0.80、95%CI 0.66〜0.97、24か月生存率 survival 生存率(survival) survival(生存率) 24.9%対10.4%。ESMOが引くハザード比 hazard ratio ハザード比(hazard ratio) hazard ratio(ハザード比) 0.76は後の更新解析)、無増悪生存(ハザード比hazard ratio ハザード比(hazard ratio)hazard ratio(ハザード比) 0.75)と奏効率 response rate 奏効率(response rate) response rate(奏効率) (26.7%対18.7%)も改善した9。二次治療second-line therapy 二次治療(second-line therapy)second-line therapy(二次治療) はFOLFOXが標準([I, A])7
- 切除不能unresectable 切除不能(unresectable)unresectable(切除不能) 例の局所の緩和も忘れない。黄疸をきたす例(胆嚢癌gallbladder cancer 胆嚢癌(gallbladder cancer)gallbladder cancer(胆嚢癌) を含む)への内視鏡的または経皮的胆道ドレナージbiliary drainage胆道ドレナージ(biliary drainage)biliary drainage(胆道ドレナージ)・ステント留置stentingステント留置(stenting)stenting(ステント留置)と、肝限局の肝内胆管癌 intrahepatic cholangiocarcinoma, ICC 肝内胆管癌(intrahepatic cholangiocarcinoma, ICC) intrahepatic cholangiocarcinoma, ICC(肝内胆管癌) に対する経動脈的化学塞栓療法transarterial chemoembolization経動脈的化学塞栓療法(transarterial chemoembolization)transarterial chemoembolization(経動脈的化学塞栓療法)などの局所療法 local therapy 局所療法(local therapy) local therapy(局所療法) (ESMO:[III, A])7、さらに全身状態・胆道感染・肝腎機能・患者目標を踏まえた放射線治療や支持緩和医療を組み合わせる(光線力学療法photodynamic therapy 光線力学療法(photodynamic therapy)photodynamic therapy(光線力学療法) は一部施設で胆道開存・局所制御の補助として検討されるが、標準全身療法 systemic therapy 全身療法(systemic therapy) systemic therapy(全身療法) の代わりにはならない)
💡 ERCPで胆道ドレナージ biliary drainage 胆道ドレナージ(biliary drainage) biliary drainage(胆道ドレナージ) ができない場合の次の選択肢: 悪性遠位胆道閉塞 distal biliary obstruction 遠位胆道閉塞(distal biliary obstruction) distal biliary obstruction(遠位胆道閉塞) では、熟練した実施体制 body plan 体制(body plan) body plan(体制) があれば超音波内視鏡下胆道ドレナージ EUS-guided biliary drainage, EUS-BD 超音波内視鏡下胆道ドレナージ(EUS-guided biliary drainage, EUS-BD) EUS-guided biliary drainage, EUS-BD(超音波内視鏡下胆道ドレナージ) を経皮経肝胆道ドレナージ percutaneous transhepatic biliary drainage, PTBD 経皮経肝胆道ドレナージ(percutaneous transhepatic biliary drainage, PTBD) percutaneous transhepatic biliary drainage, PTBD(経皮経肝胆道ドレナージ) より推奨する。肝門部閉塞に対する肝胃吻合 hepaticogastrostomy 肝胃吻合(hepaticogastrostomy) hepaticogastrostomy(肝胃吻合) は、左肝管left hepatic duct 左肝管(left hepatic duct)left hepatic duct(左肝管) が拡張し、ERCPや経皮経肝法でも十分に排液 drainage (fluid) 排液(drainage (fluid)) drainage (fluid)(排液) できない切除不能 unresectable 切除不能(unresectable) unresectable(切除不能) 例を対象に、高症例数の専門施設で検討する10。
⚠️ 講義スライド slide スライド(slide) slide(スライド) が全身化学療法 systemic chemotherapy 全身化学療法(systemic chemotherapy) systemic chemotherapy(全身化学療法) を「フルオロピリミジンfluoropyrimidine フルオロピリミジン(fluoropyrimidine)fluoropyrimidine(フルオロピリミジン) 系」と書いているのは旧い。 現在の一次治療の骨格はシスプラチン+ゲムシタビン gemcitabine ゲムシタビン(gemcitabine) gemcitabine(ゲムシタビン) であり、フルオロピリミジンfluoropyrimidine フルオロピリミジン(fluoropyrimidine)fluoropyrimidine(フルオロピリミジン) 系(FOLFOX)は二次治療second-line therapy二次治療(second-line therapy)second-line therapy(二次治療)の位置にある。7
⭐ 「切除できるか」より「R0で切除できるか」。 肝門部胆管癌perihilar cholangiocarcinoma 肝門部胆管癌(perihilar cholangiocarcinoma)perihilar cholangiocarcinoma(肝門部胆管癌) では、切除可能resectable 切除可能(resectable)resectable(切除可能) な状態で受診するのは40%未満で、そのうち約半数が開腹時に切除不能 unresectable 切除不能(unresectable) unresectable(切除不能) と判明する。R0切除R0 resection R0切除(R0 resection)R0 resection(R0切除) が得られた症例の5年全生存率 5-year overall survival 5年全生存率(5-year overall survival) 5-year overall survival(5年全生存率) は45%に達しうるのに対し、断端陽性positive surgical margin 断端陽性(positive surgical margin)positive surgical margin(断端陽性) (R1/R2)では0〜23%と報告されている。1
⚠️ ペムブロリズマブpembrolizumab ペムブロリズマブ(pembrolizumab)pembrolizumab(ペムブロリズマブ) 併用(KEYNOTE-966)の上乗せ add-on (incremental benefit) 上乗せ(add-on (incremental benefit)) add-on (incremental benefit)(上乗せ) 幅は大きくない。 未治療の進行胆道癌 biliary tract cancer 胆道癌(biliary tract cancer) biliary tract cancer(胆道癌) 1,069例で、全生存期間overall survival, OS 全生存期間(overall survival, OS)overall survival, OS(全生存期間) 中央値は併用群12.7か月対プラセボ群10.9か月(ハザード比hazard ratio ハザード比(hazard ratio)hazard ratio(ハザード比) 0.83、95%CI 0.72〜0.95、片側p=0.0034)。原著自身の結論 conclusion 結論(conclusion) conclusion(結論) も「新たな治療選択 therapeutic options 治療選択(therapeutic options) therapeutic options(治療選択) 肢になりうる」という書き方である11。推奨の強さと効果量の大きさは別に読む——ESMOはこの効果量のうえで2025年中間更新においてこの併用を[I, A]で推奨している8(2023年版にペムブロリズマブ pembrolizumab ペムブロリズマブ(pembrolizumab) pembrolizumab(ペムブロリズマブ) 併用が含まれないのは2022年12月公開時点では試験結果が出ていなかったためである7)。
💡 切除不能unresectable 切除不能(unresectable)unresectable(切除不能) 例でも分子標的が変える余地がある。ESMOは一次治療の前ないし治療中に分子プロファイリング molecular profiling分子プロファイリング(molecular profiling) molecular profiling(分子プロファイリング)を行い、パネルにFGFR2・IDH1・HER2/neu・BRAFを含めるべきとしている7。二次治療second-line therapy 二次治療(second-line therapy)second-line therapy(二次治療) 以降ではFGFR2融合・再構成に対するフチバチニブ・ペミガチニブが推奨され([III, A])、HER2過剰発現 overexpression過剰発現(overexpression) overexpression(過剰発現)・増幅にはトラスツズマブ デルクステカンtrastuzumab deruxtecanトラスツズマブ デルクステカン(trastuzumab deruxtecan)trastuzumab deruxtecan(トラスツズマブ デルクステカン)が考慮される8。既治療の進行胆管癌 cholangiocarcinoma 胆管癌(cholangiocarcinoma) cholangiocarcinoma(胆管癌) を対象とした第2相FIGHT-202試験でも、ペミガチニブはFGFR2融合・再構成をもつコホートでのみ奏効 (treatment) response 奏効((treatment) response) (treatment) response(奏効) が得られ、他のFGF/FGFR異常群や異常なし群では奏効 (treatment) response 奏効((treatment) response) (treatment) response(奏効) がなかった12。
2. 胆嚢癌
- 胆嚢粘膜から発生し、女性に多い
- 大部分は腺癌、一部は扁平上皮癌
危険因子:
- 長期の胆石症cholelithiasis (gallstone disease)胆石症(cholelithiasis (gallstone disease))cholelithiasis (gallstone disease)(胆石症)(特に大きな結石)・慢性胆嚢炎chronic cholecystitis慢性胆嚢炎(chronic cholecystitis)chronic cholecystitis(慢性胆嚢炎)/胆管炎、総胆管結石症choledocholithiasis総胆管結石症(choledocholithiasis)choledocholithiasis(総胆管結石症)
- 膵・胆管合流異常、磁器様胆嚢porcelain gallbladder磁器様胆嚢(porcelain gallbladder)porcelain gallbladder(磁器様胆嚢)(癌リスクは石灰化様式で異なるため、石灰化があるだけで一律に癌または手術適応とはしない)
- 径1 cm(10 mm)を超える胆嚢ポリープ gallbladder polyp胆嚢ポリープ(gallbladder polyp) gallbladder polyp(胆嚢ポリープ)、増大、広基性wide-based (broad-based) 広基性(wide-based (broad-based))wide-based (broad-based)(広基性) ポリープは悪性リスクを評価し、追加の画像検査と胆嚢摘出術 Cholecystectomy 胆嚢摘出術(Cholecystectomy) Cholecystectomy(胆嚢摘出術) の契機とすべきとされる2
臨床像:
- 早期は無症候性
- 胆石疝痛biliary colic胆石疝痛(biliary colic)biliary colic(胆石疝痛)、慢性胆嚢炎chronic cholecystitis 慢性胆嚢炎(chronic cholecystitis)chronic cholecystitis(慢性胆嚢炎) 様の症状
- Courvoisier徴候Courvoisier sign Courvoisier徴候(Courvoisier sign)Courvoisier sign(Courvoisier徴候) (無痛性・非圧痛性に触知できる腫大胆嚢) — 講義スライド slide スライド(slide) slide(スライド) は胆嚢癌 gallbladder cancer 胆嚢癌(gallbladder cancer) gallbladder cancer(胆嚢癌) の臨床像にもこれを挙げている。ただし⚠️ これを胆嚢癌 gallbladder cancer 胆嚢癌(gallbladder cancer) gallbladder cancer(胆嚢癌) の代表像として覚えない。 症状は胆石疝痛 biliary colic 胆石疝痛(biliary colic) biliary colic(胆石疝痛) と誤られやすく、新規診断の半数超は良性疾患として胆嚢摘出したあとの偶発診断である2
- 非特異的症状(右季肋部痛right upper quadrant pain (RUQ pain)右季肋部痛(right upper quadrant pain (RUQ pain))right upper quadrant pain (RUQ pain)(右季肋部痛)・腹痛、体重減少、悪心、倦怠感、進行例では黄疸・腫瘤・腹水)
診断:
- 経腹壁transabdominal 経腹壁(transabdominal)transabdominal(経腹壁) US(胆嚢内腫瘤、不整な壁肥厚、壁層構造の消失、閉塞部位の同定、胆嚢/胆管拡張bile duct dilatation胆管拡張(bile duct dilatation)bile duct dilatation(胆管拡張)、局所転移)
- 造影CT(肝浸潤、リンパ節、腹膜・遠隔転移の検索)、胸部CT(病期診断staging病期診断(staging)staging(病期診断))、MRI/MRCP(胆管浸潤と血管解剖の把握 grasp把握(grasp) grasp(把握))
- ERCP(診断に必須ではないが胆管ブラッシング bile duct brushing胆管ブラッシング(bile duct brushing) bile duct brushing(胆管ブラッシング)/生検が可能)
- PET検査(他検査不十分時+病期診断 staging病期診断(staging) staging(病期診断))
- ⚠️ 切除可能resectable 切除可能(resectable)resectable(切除可能) と考えられる病変では、腫瘍播種tumor seeding 腫瘍播種(tumor seeding)tumor seeding(腫瘍播種) を招き得る経皮的生検 percutaneous biopsy 経皮的生検(percutaneous biopsy) percutaneous biopsy(経皮的生検) を安易に行わず、手術戦略を肝胆膵外科 hepato-pancreato-biliary surgery 肝胆膵外科(hepato-pancreato-biliary surgery) hepato-pancreato-biliary surgery(肝胆膵外科) チームで決める。一方、切除不能unresectable切除不能(unresectable)unresectable(切除不能)・転移性で全身療法 systemic therapy 全身療法(systemic therapy) systemic therapy(全身療法) を行う場合は組織診断を得る
治療:
- 術前に強い疑いがあれば外科的探索surgical exploration 外科的探索(surgical exploration)surgical exploration(外科的探索) と切除へ進む。根治的胆嚢摘出術radical cholecystectomy 根治的胆嚢摘出術(radical cholecystectomy)radical cholecystectomy(根治的胆嚢摘出術) には病期診断staging 病期診断(staging)staging(病期診断) のための腹腔鏡、肝切除hepatectomy (liver resection)肝切除(hepatectomy (liver resection))hepatectomy (liver resection)(肝切除)、所属リンパ節郭清が含まれ、目標はR0切除 R0 resection R0切除(R0 resection) R0 resection(R0切除) である2。⚠️ ただし根治切除 curative resection 根治切除(curative resection) curative resection(根治切除) そのものを腹腔鏡下 laparoscopic 腹腔鏡下(laparoscopic) laparoscopic(腹腔鏡下) で完遂 completion (of a treatment course) 完遂(completion (of a treatment course)) completion (of a treatment course)(完遂) することを標準とは書けない——低侵襲手術 minimally invasive technique 低侵襲手術(minimally invasive technique) minimally invasive technique(低侵襲手術) の位置づけは施設経験と症例選択に依存し、優越性superiority 優越性(superiority)superiority(優越性) は確立していない
まず根治的胆嚢摘出術radical cholecystectomy 根治的胆嚢摘出術(radical cholecystectomy)radical cholecystectomy(根治的胆嚢摘出術) とは何かを定めておく。IHPBA-APHPBAの2024年国際合意は、この術式の呼称を根治的胆嚢摘出術 radical cholecystectomy 根治的胆嚢摘出術(radical cholecystectomy) radical cholecystectomy(根治的胆嚢摘出術) に統一したうえで、①原発巣 primary tumor 原発巣(primary tumor) primary tumor(原発巣) と一塊 en bloc 一塊(en bloc) en bloc(一塊) にした肝切除 hepatectomy (liver resection) 肝切除(hepatectomy (liver resection)) hepatectomy (liver resection)(肝切除) (範囲はT1aの「肝切除hepatectomy (liver resection) 肝切除(hepatectomy (liver resection))hepatectomy (liver resection)(肝切除) なし」から楔状切除 wedge resection楔状切除(wedge resection) wedge resection(楔状切除)・S4b+S5区域切除 segmentectomy区域切除(segmentectomy) segmentectomy(区域切除)・大量肝切除 hepatectomy (liver resection) 肝切除(hepatectomy (liver resection)) hepatectomy (liver resection)(肝切除) まで幅がある)と②T1b以降で行う完全な肝十二指腸間膜リンパ節郭清 hepatoduodenal ligament lymph node dissection肝十二指腸間膜リンパ節郭清(hepatoduodenal ligament lymph node dissection) hepatoduodenal ligament lymph node dissection(肝十二指腸間膜リンパ節郭清)の組合せと定義した。胆管切除はR0達成に必要な場合に行い、ルーチンには追加しない。「拡大」はこの標準を超える範囲(大量肝切除 hepatectomy (liver resection)肝切除(hepatectomy (liver resection)) hepatectomy (liver resection)(肝切除)、肝外胆管extrahepatic bile duct 肝外胆管(extrahepatic bile duct)extrahepatic bile duct(肝外胆管) 切除、十二指腸・結腸などの隣接臓器合併切除、血管合併切除combined vascular resection血管合併切除(combined vascular resection)combined vascular resection(血管合併切除)、腹腔動脈celiac trunk 腹腔動脈(celiac trunk)celiac trunk(腹腔動脈) 周囲・傍大動脈para-aortic 傍大動脈(para-aortic)para-aortic(傍大動脈) へのリンパ節郭清拡大)を指す語として使い、標準術式の呼称には使わない。13
Tステージ Stage ステージ(Stage) Stage(ステージ) 別の術式(T分類はAJCC第8版に基づく。以下の術式は主にIHPBA-APHPBA 2024の合意による):
| T分類 | 浸潤範囲 | 術式 |
|---|---|---|
| T1a | 粘膜固有層lamina propria 粘膜固有層(lamina propria)lamina propria(粘膜固有層) まで | 単純胆嚢摘出術simple cholecystectomy 単純胆嚢摘出術(simple cholecystectomy)simple cholecystectomy(単純胆嚢摘出術) (肝切除hepatectomy (liver resection) 肝切除(hepatectomy (liver resection))hepatectomy (liver resection)(肝切除) もリンパ節郭清も不要)13 |
| T1b | 筋層浸潤 | 根治的胆嚢摘出術radical cholecystectomy 根治的胆嚢摘出術(radical cholecystectomy)radical cholecystectomy(根治的胆嚢摘出術) (肝切除hepatectomy (liver resection) 肝切除(hepatectomy (liver resection))hepatectomy (liver resection)(肝切除) +肝十二指腸間膜リンパ節郭清 hepatoduodenal ligament lymph node dissection肝十二指腸間膜リンパ節郭清(hepatoduodenal ligament lymph node dissection) hepatoduodenal ligament lymph node dissection(肝十二指腸間膜リンパ節郭清))1413 |
| T2a | 筋周囲結合組織perimuscular connective tissue 筋周囲結合組織(perimuscular connective tissue)perimuscular connective tissue(筋周囲結合組織) まで浸潤(腹膜側) | 講義スライド slide スライド(slide) slide(スライド) は「肝床gallbladder fossa (liver bed) 肝床(gallbladder fossa (liver bed))gallbladder fossa (liver bed)(肝床) の楔状切除 wedge resection楔状切除(wedge resection) wedge resection(楔状切除)、またはS4b+S5区域切除 segmentectomy 区域切除(segmentectomy) segmentectomy(区域切除) +リンパ節郭清」の2択を挙げる。IHPBA-APHPBA 2024はT2全体について「断端陰性の楔状切除 wedge resection 楔状切除(wedge resection) wedge resection(楔状切除) で足りる」ことに合意した13 |
| T2b | 筋周囲結合組織perimuscular connective tissue 筋周囲結合組織(perimuscular connective tissue)perimuscular connective tissue(筋周囲結合組織) まで浸潤(肝臓側) | 同上。ただし肝臓側は予後が悪く、術後補助化学療法adjuvant chemotherapy 術後補助化学療法(adjuvant chemotherapy)adjuvant chemotherapy(術後補助化学療法) の対象に挙げられる2 |
| T3 | 漿膜穿破serosal penetration漿膜穿破(serosal penetration)serosal penetration(漿膜穿破)、肝や他臓器へ浸潤 | 楔状切除wedge resection 楔状切除(wedge resection)wedge resection(楔状切除) とS4b+S5区域切除 segmentectomy 区域切除(segmentectomy) segmentectomy(区域切除) で専門家 expert 専門家(expert) expert(専門家) の支持が拮抗し、どちらも許容可能とされた。目標はR0切除 R0 resection R0切除(R0 resection) R0 resection(R0切除) で、術者operator (person performing the procedure) 術者(operator (person performing the procedure))operator (person performing the procedure)(術者) の裁量で範囲を決める13 |
| T4 | 門脈・肝動脈hepatic artery 肝動脈(hepatic artery)hepatic artery(肝動脈) への浸潤、または複数の肝外 extrahepatic 肝外(extrahepatic) extrahepatic(肝外) 臓器浸潤 organ infiltration臓器浸潤(organ infiltration) organ infiltration(臓器浸潤) | 講義スライド slide スライド(slide) slide(スライド) は「根治的肝切除 hepatectomy (liver resection) 肝切除(hepatectomy (liver resection)) hepatectomy (liver resection)(肝切除) (例:右肝切除 right hepatectomy右肝切除(right hepatectomy) right hepatectomy(右肝切除))」と書くが、一律の定型術式はなく、R0切除R0 resection R0切除(R0 resection)R0 resection(R0切除) 可能性と全身状態から切除適応を慎重に判断する。血管合併切除combined vascular resection 血管合併切除(combined vascular resection)combined vascular resection(血管合併切除) や多臓器合併切除 multivisceral resection 多臓器合併切除(multivisceral resection) multivisceral resection(多臓器合併切除) へ拡大しても生存が改善することはまれだ、というのが合意文書の記述である13 |
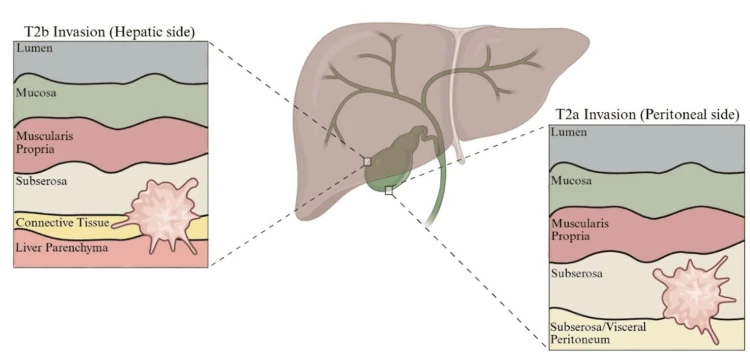
出典:Ahmad CMほか(2026)「T2b Gallbladder Adenocarcinoma Diagnosed by Frozen Section With High-Grade Dysplasia at the Cystic Duct Margin: Diagnostic and Prognostic Considerations」Fig. 1(CC BY 4.0)。著者作成の模式図をJPEGからWebPに変換。左は肝臓側T2b、右は腹膜側T2aを示し、いずれも筋周囲結合組織 perimuscular connective tissue 筋周囲結合組織(perimuscular connective tissue) perimuscular connective tissue(筋周囲結合組織) にとどまる。
⚠️ T2を「T2」のままにしない。 AJCC第8版はT2を腫瘍の位置でT2a(腹膜側)とT2b(肝臓側)に分けた。根拠は、肝臓側の腫瘍のほうが脈管浸潤 vascular invasion 脈管浸潤(vascular invasion) vascular invasion(脈管浸潤) (51%対19%)・神経浸潤perineural invasion 神経浸潤(perineural invasion)perineural invasion(神経浸潤) (33%対8%)・リンパ節転移(40%対17%)が多く、5年生存率も42.6%対64.7%と低いという知見である。講義スライド slide スライド(slide) slide(スライド) のように「T1/T2/T3/T4」の4段だけで覚えると、この区別と、T1をT1a/T1bに分ける線引きの両方が抜ける。15
⚠️ 楔状切除wedge resection 楔状切除(wedge resection)wedge resection(楔状切除) の切除幅として言われる「2 cm」「3 cm」といったマージン margin マージン(margin) margin(マージン) は恣意的で、必要なのは病理学的に断端陰性になる幅である、というのが合意の立場である。13
💡 胆嚢癌gallbladder cancer 胆嚢癌(gallbladder cancer)gallbladder cancer(胆嚢癌) の術式はT分類だけで固定せず、肝・胆管・血管への進展、リンパ節転移、R0切除R0 resection R0切除(R0 resection)R0 resection(R0切除) 可能性、全身状態を踏まえて決める。2 なお大動脈周囲(16b1)リンパ節転移は遠隔転移として扱い、そこに転移がある症例への手術は標準としては推奨されない。13
偶発胆嚢癌
- 定義: 術前に疑われていなかった胆嚢癌 gallbladder cancer 胆嚢癌(gallbladder cancer) gallbladder cancer(胆嚢癌) が、良性疾患として行った胆嚢摘出術 Cholecystectomy 胆嚢摘出術(Cholecystectomy) Cholecystectomy(胆嚢摘出術) の病理標本で偶然 chance 偶然(chance) chance(偶然) 見つかったもの。術中迅速診断intraoperative frozen section 術中迅速診断(intraoperative frozen section)intraoperative frozen section(術中迅速診断) で判明した場合も含める13
- 頻度: 全胆嚢摘出標本の0.25〜0.89%に認められ14、胆嚢癌gallbladder cancer 胆嚢癌(gallbladder cancer)gallbladder cancer(胆嚢癌) の新規診断の半数超がこの経路で見つかる2。iGBCの80%超はpT2またはpT3である13
- 追加切除(完成根治的胆嚢摘出術completion radical cholecystectomy完成根治的胆嚢摘出術(completion radical cholecystectomy)completion radical cholecystectomy(完成根治的胆嚢摘出術))の適応は深達度 depth of invasion 深達度(depth of invasion) depth of invasion(深達度) で決まる(初回標本の深達度 depth of invasion深達度(depth of invasion) depth of invasion(深達度)、断端、胆嚢穿孔gallbladder perforation胆嚢穿孔(gallbladder perforation)gallbladder perforation(胆嚢穿孔)、ポート部汚染を再評価する)14
| 初回標本の深達度 depth of invasion深達度(depth of invasion) depth of invasion(深達度) | 方針 | 根拠となる数字 |
|---|---|---|
| pT1a | 追加切除は不要で、経過観察してよい | 5年生存率はほぼ100% |
| pT1b以上 | 追加切除を提示すべき | pT1bでも5年生存率は84.8%へ低下し、リンパ節転移・遺残病変residual lesion 遺残病変(residual lesion)residual lesion(遺残病変) が約9.9%にみられる |
- ⚠️ T1bで「議論がある」のは追加切除の要否ではない。 系統的レビューは「筋層に達するT1b以上では再切除が推奨される」としたうえで、議論が残るのは再切除の術式・範囲・時期であると書き分けている14。国際合意(IHPBA-APHPBA 2024)でも、高齢・全身麻酔の高リスク・重篤な併存疾患 comorbidity 併存疾患(comorbidity) comorbidity(併存疾患) では適応を絞りうるとの議論はあったが、その例外は推奨としては採択されなかった13
- ⚠️ ポート部の切除はルーチンには行わない。 初回手術時の穿孔は播種リスクを高め、ポート部転移は約10%に生じるが、ポート部切除は再発を減らさず生存も改善せず、最大8%に瘢痕ヘルニア incisional hernia 瘢痕ヘルニア(incisional hernia) incisional hernia(瘢痕ヘルニア) を生じる。ポート部再発は通常、腹膜播種peritoneal dissemination 腹膜播種(peritoneal dissemination)peritoneal dissemination(腹膜播種) の表れである1413
- 術後補助化学療法adjuvant chemotherapy術後補助化学療法(adjuvant chemotherapy)adjuvant chemotherapy(術後補助化学療法)は、局所進行(T3・T4)、肝臓側のT2、リンパ節転移陽性、R1切除の症例で利益が期待される2
💡 病期分類staging 病期分類(staging)staging(病期分類) の版に注意。 胆嚢癌gallbladder cancer 胆嚢癌(gallbladder cancer)gallbladder cancer(胆嚢癌) のAJCC病期分類 staging 病期分類(staging) staging(病期分類) は、部位別のAJCC Version 9が出るまで第8版に基づく。2025年のUICC TNM第9版は早期の病期グルーピングを細分し、Stage IA=T1aN0M0/IB=T1bN0M0、IIA=T2aN0M0/IIB=T2bN0M0とした。ただしこうした細分化で予後判別能 discriminative ability 判別能(discriminative ability) discriminative ability(判別能) が大きく上がったわけではなく、全生存overall survival (OS) 全生存(overall survival (OS))overall survival (OS)(全生存) のC統計量 C-statistic C統計量(C-statistic) C-statistic(C統計量) は第8版0.665・第7版0.663とほぼ変わらない。15
まとめ
- 胆管癌cholangiocarcinoma 胆管癌(cholangiocarcinoma)cholangiocarcinoma(胆管癌) は発生部位で分類し、遠位では膵頭十二指腸切除 pancreaticoduodenectomy膵頭十二指腸切除(pancreaticoduodenectomy) pancreaticoduodenectomy(膵頭十二指腸切除)、肝門部では拡大右肝切除 extended right hepatectomy 拡大右肝切除(extended right hepatectomy) extended right hepatectomy(拡大右肝切除) または左肝切除 left hepatectomy 左肝切除(left hepatectomy) left hepatectomy(左肝切除) に胆管切除・肝門部リンパ節郭清hepatic hilar lymph node dissection肝門部リンパ節郭清(hepatic hilar lymph node dissection)hepatic hilar lymph node dissection(肝門部リンパ節郭清)・胆道再建biliary reconstruction 胆道再建(biliary reconstruction)biliary reconstruction(胆道再建) (+尾状葉切除 caudate lobectomy尾状葉切除(caudate lobectomy) caudate lobectomy(尾状葉切除))を加える。将来残肝future liver remnant (FLR) 将来残肝(future liver remnant (FLR))future liver remnant (FLR)(将来残肝) 容量が不足する場合は門脈塞栓術 portal vein embolization 門脈塞栓術(portal vein embolization) portal vein embolization(門脈塞栓術) を検討する。14
- Bismuth-Corlette分類Bismuth-Corlette classification Bismuth-Corlette分類(Bismuth-Corlette classification)Bismuth-Corlette classification(Bismuth-Corlette分類) は肝門部型 perihilar (hilar) type 肝門部型(perihilar (hilar) type) perihilar (hilar) type(肝門部型) の胆管進展を整理する分類だが、切除可能性resectability 切除可能性(resectability)resectability(切除可能性) は予測しない(AJCC病期分類 staging 病期分類(staging) staging(病期分類) も同じ)。可否は多職種カンファレンスで決める。1
- 進行胆道癌 biliary tract cancer 胆道癌(biliary tract cancer) biliary tract cancer(胆道癌) では閉塞性黄疸 obstructive jaundice 閉塞性黄疸(obstructive jaundice) obstructive jaundice(閉塞性黄疸) や腫大胆嚢を認めることがあるが、胆嚢癌gallbladder cancer 胆嚢癌(gallbladder cancer)gallbladder cancer(胆嚢癌) は新規診断の半数超が胆嚢摘出後の偶発診断である。2
- MRCPは非侵襲的な胆道・進展範囲評価に用い、胆道ドレナージbiliary drainage 胆道ドレナージ(biliary drainage)biliary drainage(胆道ドレナージ) の前に撮る。術前胆道ドレナージ biliary drainage 胆道ドレナージ(biliary drainage) biliary drainage(胆道ドレナージ) (内視鏡的・経皮経肝)の手技選択は施設方針と解剖で選ぶ。CA19-9は高ビリルビン血症 Hyperbilirubinemia 高ビリルビン血症(Hyperbilirubinemia) Hyperbilirubinemia(高ビリルビン血症) で偽高値 falsely elevated (value) 偽高値(falsely elevated (value)) falsely elevated (value)(偽高値) になる。15
- 外科的切除が唯一の根治手段だが、予後は病期とR0切除 R0 resection R0切除(R0 resection) R0 resection(R0切除) 可能性で大きく異なる。肝門部胆管癌perihilar cholangiocarcinoma 肝門部胆管癌(perihilar cholangiocarcinoma)perihilar cholangiocarcinoma(肝門部胆管癌) ではR0で5年全生存率 5-year overall survival 5年全生存率(5-year overall survival) 5-year overall survival(5年全生存率) 45%に対し、断端陽性positive surgical margin 断端陽性(positive surgical margin)positive surgical margin(断端陽性) では0〜23%。肝移植liver transplantation 肝移植(liver transplantation)liver transplantation(肝移植) は厳格なプロトコルに適合する一部症例に限られる。12
- 胆嚢癌gallbladder cancer 胆嚢癌(gallbladder cancer)gallbladder cancer(胆嚢癌) はT分類をAJCC第8版(T1a/T1b、T2a腹膜側/T2b肝臓側)で読む。pT1aなら単純胆嚢摘出術 simple cholecystectomy 単純胆嚢摘出術(simple cholecystectomy) simple cholecystectomy(単純胆嚢摘出術) で足り、pT1b以上では追加の根治的胆嚢摘出術 radical cholecystectomy 根治的胆嚢摘出術(radical cholecystectomy) radical cholecystectomy(根治的胆嚢摘出術) (肝切除hepatectomy (liver resection) 肝切除(hepatectomy (liver resection))hepatectomy (liver resection)(肝切除) +肝十二指腸間膜リンパ節郭清 hepatoduodenal ligament lymph node dissection肝十二指腸間膜リンパ節郭清(hepatoduodenal ligament lymph node dissection) hepatoduodenal ligament lymph node dissection(肝十二指腸間膜リンパ節郭清))を提示すべきとされる(議論が残るのは術式・範囲・時期)。ポート部のルーチン切除は不要。1413
- 術後補助療法postoperative adjuvant therapy 術後補助療法(postoperative adjuvant therapy)postoperative adjuvant therapy(術後補助療法) はカペシタビン capecitabine カペシタビン(capecitabine) capecitabine(カペシタビン) (ESMO [II, A])。切除不能unresectable 切除不能(unresectable)unresectable(切除不能) 例の一次治療はゲムシタビン gemcitabine ゲムシタビン(gemcitabine) gemcitabine(ゲムシタビン) +シスプラチンに免疫チェックポイント阻害薬 immune checkpoint inhibitor (ICI) 免疫チェックポイント阻害薬(immune checkpoint inhibitor (ICI)) immune checkpoint inhibitor (ICI)(免疫チェックポイント阻害薬) を加える形で、ESMOは2025年中間更新でデュルバルマブ durvalumab デュルバルマブ(durvalumab) durvalumab(デュルバルマブ) 併用(TOPAZ-1)とペムブロリズマブ pembrolizumab ペムブロリズマブ(pembrolizumab) pembrolizumab(ペムブロリズマブ) 併用(KEYNOTE-966)の両方を[I, A]として挙げ、分子プロファイリングmolecular profiling 分子プロファイリング(molecular profiling)molecular profiling(分子プロファイリング) (FGFR2融合に対するペミガチニブ等)へつなげる。911812
出典
- 1.Current Perspectives on the Surgical Management of Perihilar Cholangiocarcinoma(Cancers・2022)全文(PMC9104954)で確認した。肝門部胆管癌は二次分枝胆管と胆嚢管合流部のあいだに発生し、胆管癌全体の50〜60%を占める。標準術式は逐語で「either a right extended hepatectomy or left hemi-hepatectomy with concomitant bile duct resection and porta hepatis lymphadenectomy with bilioenteric reconstruction」であり、尾状葉切除は断端陰性率と生存を改善し有意な合併症増加を伴わないとする。切除可能例は40%未満で、そのうち約50%が開腹時に切除不能と判明する。R0切除例の5年全生存率は45%に達しうる一方、断端陽性(R1/R2)では0〜23%。AJCC病期分類もBismuth-Corlette分類も切除可能性を予測しないとし、切除の可否は多職種カンファレンスで決めるべきとする。CEAとCA19-9は胆管癌に特異的ではなく予後情報にとどまり、CA19-9は高ビリルビン血症で偽高値になりうる。MRCPは直接胆道造影より病期診断能が高い可能性があり、アーチファクトを避けるため胆道ドレナージ・ステント留置の前に撮るのが望ましい。PET-CTはCT単独より所属リンパ節・遠隔転移の検出精度が高く、約25%で方針を変えうる。⚠️ Bismuth-Corlette分類の各型の定義は本文になく図2の画像内にのみ置かれており、その画像は取得できていない。閲覧 2026-09-21
- 2.Gallbladder Cancer: Diagnosis, Surgical Management, and Adjuvant Therapies(Surgical Clinics of North America・2019)抄録(PubMed、PMID 30846038)で確認した。逐語で「Symptoms may be misdiagnosed as biliary colic; over half of new diagnoses are made after laparoscopic cholecystectomy for presumed benign disease.」「Gallbladder polyps >1 cm should prompt additional imaging and cholecystectomy.」「For GBC diagnosed after cholecystectomy, tumors T1b and greater necessitate radical cholecystectomy.」「Radical cholecystectomy includes staging laparoscopy, hepatic resection, and locoregional lymph node clearance to achieve R0 resection.」「Patients with locally advanced disease (T3 or T4), hepatic-sided T2 tumors, node positivity, or R1 resection may benefit from adjuvant chemotherapy.」と述べる。⚠️ 本文は購読誌にありUnpaywallもoa_status closed・リポジトリ版なしで、抄録以外は取得できていない。閲覧 2026-09-21
- 3.British Society of Gastroenterology guidelines for the diagnosis and management of cholangiocarcinoma(British Society of Gastroenterology・2024)全文(Gut 2024;73:16-46)で確認した。胆管癌の危険因子として原発性硬化性胆管炎、胆管結石、先天性総胆管嚢胞、Caroli病、肝吸虫、慢性肝炎・肝硬変などを挙げる。WHO第5版に沿った病理分類では胆管内乳頭状腫瘍と胆道上皮内腫瘍などを前癌病変として、胆管腺腫などの良性病変とは区別する。胆管内乳頭状腫瘍は浸潤癌を伴うことがあり、その割合は病型により異なる。閲覧 2026-10-12
- 4.The role of portal vein embolization in the surgical management of primary hepatobiliary cancers. A systematic review(European Journal of Surgical Oncology・2017)1990〜2015年の40論文・2,144例の系統的レビューで、残肝容量(FLR)不足を伴う原発性肝胆道悪性腫瘍に対する門脈塞栓術後の肝切除率は肝細胞癌90%、肝門部胆管癌86%であった。門脈塞栓術は不十分なFLRを補い、大量肝切除を可能にする手段として位置づけられる。閲覧 2026-08-26
- 5.Endoscopic and percutaneous preoperative biliary drainage in patients with suspected hilar cholangiocarcinoma(Journal of Gastrointestinal Surgery・2010)肝門部胆管癌が疑われ大量肝切除を要した115例のうち術前胆道ドレナージを受けた101例の後ろ向き解析で、内視鏡的ドレナージ群は経皮経肝ドレナージ群より感染性合併症が有意に多かった(48%対9%)。術前胆道ドレナージの手技選択には内視鏡・経皮のいずれにも一長一短があり、施設方針で選ぶ根拠を示した。閲覧 2026-08-26
- 6.Diagnostic work-up of bile duct strictures: European Society of Gastrointestinal Endoscopy (ESGE) Guideline(European Society of Gastrointestinal Endoscopy・2025)学会ガイドラインの推奨を確認した。標準的なERCP検体採取で診断が確定しない胆管狭窄では、選択例に胆道鏡直視下の標的生検を追加することを提案する。閲覧 2026-10-12
- 7.Biliary tract cancer: ESMO Clinical Practice Guideline for diagnosis, treatment and follow-up(European Society for Medical Oncology(ESMO)・2023)UCL Discoveryに置かれた組版前原稿(Journal Pre-proof。誌上版はAnn Oncol 2023;34:127-140)で確認した。一次治療の推奨は「Cisplatin-gemcitabine is recommended as SoC in the first-line setting for patients with a PS of 0-1 [I, A]」「The combination of cisplatin-gemcitabine with durvalumab should be considered in first-line BTC [I, A; ESMO-MCBS v1.1 score 4]」で、根拠はTOPAZ-1(全生存のハザード比0.76、95%CI 0.64-0.91)。二次治療はFOLFOXがSoC [I, A]、術後補助療法はカペシタビン [II, A]。治療アルゴリズム図の脚注hは同じ併用を「is recommended for first-line treatment [I, A]」と書いており、推奨一覧の「should be considered」と文言が一致しない。分子プロファイリングは一次治療前ないし治療中に行い、パネルにFGFR2・IDH1・HER2/neu・BRAFを含めるべきとする。⚠️ 本ガイドラインは2022年12月に公開されたものでKEYNOTE-966の結果は含まれていない。閲覧 2026-09-21
- 8.ESMO Clinical Practice Guideline interim update on the management of biliary tract cancer(European Society for Medical Oncology(ESMO)・2025)全文(PMC11846563、Europe PMCのfullTextXML)で確認した。序文は逐語で "This interim update provides new recommendations for the following ESMO Clinical Practice Guideline (CPG): Biliary tract cancer" と述べ、2023年版を更新する文書であることを明示する。一次治療の推奨は逐語で "Cisplatin–gemcitabine–durvalumab and cisplatin–gemcitabine–pembrolizumab are recommended as first-line therapy [I, A]." であり、本文は "Cisplatin–gemcitabine combined with either pembrolizumab or durvalumab is a viable option for first-line treatment. At present, there are no discernible clinical, biochemical or molecular biomarkers, nor any notable differences in efficacy or toxicity, favouring one immune checkpoint inhibitor over the other." と、2剤を選び分ける指標が無いことを明記する。KEYNOTE-966は1,069例で全生存期間中央値12.7か月対10.9か月(ハザード比0.83、95%CI 0.72-0.95、P=0.0034)。二次治療以降はFGFR2融合・再構成へのフチバチニブ・ペミガチニブが[III, A]、HER2過剰発現・増幅へのトラスツズマブ デルクステカンは should be considered。ESMO Openは10巻1号104003(Crossrefのissuedは2025年1月)。閲覧 2026-09-21
- 9.Durvalumab plus Gemcitabine and Cisplatin in Advanced Biliary Tract Cancer(NEJM Evidence・2022)抄録(PMID 38319896)で確認した。未治療の切除不能・転移性・再発胆道癌685例を対象とした二重盲検プラセボ対照第3相TOPAZ-1試験で、ゲムシタビン+シスプラチンへのデュルバルマブ追加は主要評価項目の全生存を改善した(ハザード比0.80、95%CI 0.66〜0.97、P=0.021。24か月生存率24.9%対10.4%)。無増悪生存のハザード比は0.75(0.63〜0.89、P=0.001)、奏効率は26.7%対18.7%、Grade 3〜4有害事象の頻度は75.7%対77.8%とほぼ同等。抄録は背景で「一次治療の標準治療(ゲムシタビン+シスプラチン)は10年以上変わっていない」と述べる。⚠️ ESMOが引く「ハザード比0.76」はこの初回解析の値ではなく、2022年に別途報告された更新解析の値である。閲覧 2026-08-26
- 10.Therapeutic endoscopic ultrasound: European Society of Gastrointestinal Endoscopy (ESGE) Guideline(European Society of Gastrointestinal Endoscopy・2022)学会ガイドラインの推奨を確認した。悪性遠位胆道閉塞でERCPが不成功の場合、施設に熟練者がいる条件で経皮経肝胆道ドレナージより超音波内視鏡下胆道ドレナージを推奨する。肝門部閉塞への肝胃吻合は、左肝管拡張がありERCPまたは経皮経肝胆道ドレナージで十分に排液できない切除不能例に限り、高症例数の専門施設で検討する。閲覧 2026-10-12
- 11.Pembrolizumab in combination with gemcitabine and cisplatin compared with gemcitabine and cisplatin alone for patients with advanced biliary tract cancer(The Lancet・2023)抄録(PMID 37075781)で確認した。未治療の切除不能・局所進行または転移性胆道癌1,069例(ECOG PS 0-1)を無作為化し、主要評価項目の全生存期間中央値はペムブロリズマブ群12.7か月(95%CI 11.5-13.6)対プラセボ群10.9か月(9.9-11.6)、ハザード比0.83(95%CI 0.72-0.95)、片側p=0.0034(有意水準p=0.0200)。Interpretationの逐語は「pembrolizumab plus gemcitabine and cisplatin could be a new treatment option for patients with previously untreated metastatic or unresectable biliary tract cancer」であり、標準治療であるとは述べていない。閲覧 2026-09-21
- 12.Pemigatinib for previously treated, locally advanced or metastatic cholangiocarcinoma: a multicentre, open-label, phase 2 study(The Lancet Oncology・2020)既治療の進行胆管癌を対象とした第2相FIGHT-202試験で、FGFR1〜3阻害薬ペミガチニブはFGFR2融合・再構成をもつコホートでのみ奏効が得られ、他のFGF/FGFR異常群・異常なし群では奏効がなかった。閲覧 2026-08-26
- 13.'IHPBA-APHPBA clinical practice guidelines': international Delphi consensus recommendations for gallbladder cancer(International Hepato-Pancreato-Biliary Association/Asia-Pacific Hepato-Pancreato-Biliary Association・2024)著者最終稿(LSHTM Research Onlineに置かれたaccepted manuscript。誌上版はHPB 2024;26:1311-1326で出版社サイトは403)で確認した。17か国45名の専門家による4ラウンドのDelphi法で、68の臨床設問のうち92.6%(63/68)で75%超の同意による合意が成立した。根治的胆嚢摘出術(radical cholecystectomy)の定義は①原発巣と一塊にした肝切除(範囲はT1aでは肝切除なし/楔状切除/S4b・S5切除/大量肝切除と幅がある)と②T1b以降の完全な肝十二指腸間膜リンパ節郭清(CS 39)。偶発胆嚢癌(iGBC)はpT1aなら5年生存率がほぼ100%で手術介入なしに経過観察できる(CS 34)、pT1bは5年生存率84.8%でリンパ節転移・遺残病変が約9.9%にみられるため追加切除を提示すべきである(CS 35。高齢・全身麻酔高リスク・重篤な併存疾患では適応を絞りうると議論されたが、例外は推奨として採択されなかった)。T2では断端陰性の楔状切除で十分との合意が得られ、T3では楔状切除とS4b・S5切除の支持が拮抗し双方を許容可能とした。ポート部切除は再発を減らさず生存も改善せず最大8%に瘢痕ヘルニアを生じるため不要(CS 51)。16b1リンパ節転移は遠隔転移として扱い手術を標準とは推奨しない。iGBCの80%超はpT2またはpT3である。⚠️ 誌上版の表は著者最終稿に含まれておらず、合意文の一覧表は参照できていない。閲覧 2026-09-21
- 14.Systematic review of management of incidental gallbladder cancer after cholecystectomy(The British Journal of Surgery・2019)抄録(PMID 30582640)で確認した。全胆嚢摘出標本の0.25〜0.89%に偶発胆嚢癌を認め、約半数がpT2、約3分の1がpT1であった。逐語で "Patients with cancers confined to the mucosa (T1a or less) had 5-year survival rates of up to 100 per cent after cholecystectomy alone. For cancers invading the muscle layer of the gallbladder wall (T1b or above), reresection is recommended. The type, extent and timing of reresection remain controversial." と述べる——議論が残るのは再切除の術式・範囲・時期であって、再切除を行うかどうかではない。初回手術時の穿孔は播種のリスクを高め、ポート部転移は約10%に生じるがポート部のルーチン切除は生存に影響しない。閲覧 2026-08-26
- 15.From Anatomical Staging to Precision Prognostication: Evolution of Gallbladder Cancer Staging Across AJCC Editions and the 2025 UICC TNM Update(Journal of Personalized Medicine・2026)全文(PMC13514314、CC BY)で確認した。胆嚢癌の病期分類の版を整理した叙述的総説で、逐語で「The 2025 UICC TNM 9th edition introduced a limited but important refinement to early GBC stage grouping, while AJCC GBC staging remains based on the AJCC 8th edition unless superseded by a disease-site-specific AJCC Version 9 protocol」と述べ、「ninth edition」という呼称はUICCのTNMマニュアルを指し胆嚢癌に固有のAJCC改訂ではないと注意する。UICC TNM 9ではStage IAがT1aN0M0、IBがT1bN0M0、IIA・IIBがT2aN0M0・T2bN0M0で、T1aとT1bが病期として分離された。T分類の変更点としてT1の細分・T2a/T2bの分離・T3/T4定義の明確化を挙げ、いずれも予後判別能の向上は限定的で、全生存のC統計量は第8版0.665・第7版0.663とほぼ変わらないと述べる。第8版でT2を腹膜側と肝臓側に分けた根拠として、肝臓側腫瘍は脈管浸潤51%対19%、神経浸潤33%対8%、リンパ節転移40%対17%(いずれもp<0.01)、3年生存52.1%対73.7%、5年生存42.6%対64.7%と予後が悪いという参照文献33の知見を挙げる。⚠️ 叙述的総説であって病期分類の原典ではなく、これらの数値も本総説が引用した値である。閲覧 2026-09-21