外科学 · O/05
食道裂孔ヘルニアと胃食道逆流症(GERD)
Hiatal hernia – GERD
🧠 食道裂孔ヘルニアhiatal hernia 食道裂孔ヘルニア(hiatal hernia)hiatal hernia(食道裂孔ヘルニア) は「裂孔が緩んで胃が胸腔に迷入 migrate/displace into 迷入(migrate/displace into) migrate/displace into(迷入) する」解剖学的異常、GERDは逆流バリア破綻を中核に一過性LES弛緩 transient lower esophageal sphincter relaxation一過性LES弛緩(transient lower esophageal sphincter relaxation) transient lower esophageal sphincter relaxation(一過性LES弛緩)、食道クリアランスesophageal clearance 食道クリアランス(esophageal clearance)esophageal clearance(食道クリアランス) 障害、知覚過敏hyperesthesia 知覚過敏(hyperesthesia)hyperesthesia(知覚過敏) などが関与する多因子病態。 両者は別物だが、滑脱型sliding type 滑脱型(sliding type)sliding type(滑脱型) ヘルニアは胃食道逆流症gastroesophageal reflux disease, GERD胃食道逆流症(gastroesophageal reflux disease, GERD)gastroesophageal reflux disease, GERD(胃食道逆流症)を合併しやすい。大きな食道裂孔ヘルニア hiatal hernia 食道裂孔ヘルニア(hiatal hernia) hiatal hernia(食道裂孔ヘルニア) は抗逆流手術 antireflux surgery 抗逆流手術(antireflux surgery) antireflux surgery(抗逆流手術) の恩恵が最も大きい群でもある。1 無症候〜軽症のII〜IV型(傍食道ヘルニアparaesophageal hernia傍食道ヘルニア(paraesophageal hernia)paraesophageal hernia(傍食道ヘルニア))では、EAES 2023は一般には保存的管理 conservative management 保存的管理(conservative management) conservative management(保存的管理) より手術を提案する一方、虚弱な患者では逆に手術より保存的管理 conservative management 保存的管理(conservative management) conservative management(保存的管理) を強く推奨している。2
0. 食道の解剖と生理
食道の壁構造・運動・周囲臓器との関係は、食道憩室esophageal diverticulum 食道憩室(esophageal diverticulum)esophageal diverticulum(食道憩室) とアカラシア achalasiaアカラシア(achalasia) achalasia(アカラシア)、食道損傷、食道腫瘍Esophageal Tumors食道腫瘍(Esophageal Tumors)Esophageal Tumors(食道腫瘍)を理解する共通の土台になる。
- 食道は咽頭〜胃をつなぐ長さ約25cmの管腔臓器、椎体レベルではC6〜T11/T12に相当。
- 蠕動により食物を咽頭から胃へ推進 propulsion 推進(propulsion) propulsion(推進) し、粘液分泌mucus secretion 粘液分泌(mucus secretion)mucus secretion(粘液分泌) で内腔を潤滑する。
解剖学的狭窄部位
- 輪状軟骨レベルcricoid cartilage 輪状軟骨レベル(cricoid cartilage)cricoid cartilage(輪状軟骨レベル) ——輪状咽頭筋 cricopharyngeus muscle (cricopharyngeal muscle) 輪状咽頭筋(cricopharyngeus muscle (cricopharyngeal muscle)) cricopharyngeus muscle (cricopharyngeal muscle)(輪状咽頭筋) による
- 大動脈弓aortic arch大動脈弓(aortic arch)aortic arch(大動脈弓)
- 左主気管支left main bronchus 左主気管支(left main bronchus)left main bronchus(左主気管支) が食道の前を横切る部位。左心房left atrium 左心房(left atrium)left atrium(左心房) の拡大も食道を後方へ圧排 mass effect 圧排(mass effect) mass effect(圧排) しうる
- 横隔膜
括約筋
| 括約筋 | 位置 |
|---|---|
| 上部食道括約筋upper esophageal sphincter上部食道括約筋(upper esophageal sphincter)upper esophageal sphincter(上部食道括約筋) | 輪状咽頭筋cricopharyngeus muscle (cricopharyngeal muscle)輪状咽頭筋(cricopharyngeus muscle (cricopharyngeal muscle))cricopharyngeus muscle (cricopharyngeal muscle)(輪状咽頭筋)・下咽頭収縮筋inferior pharyngeal constrictor muscle 下咽頭収縮筋(inferior pharyngeal constrictor muscle)inferior pharyngeal constrictor muscle(下咽頭収縮筋) のレベル |
| 下部食道括約筋lower esophageal sphincter, LES下部食道括約筋(lower esophageal sphincter, LES)lower esophageal sphincter, LES(下部食道括約筋) | 横隔膜のレベル |
切歯incisors 切歯(incisors)incisors(切歯) からの距離は、上部食道括約筋upper esophageal sphincter 上部食道括約筋(upper esophageal sphincter)upper esophageal sphincter(上部食道括約筋) が約15 cm、胃食道接合部gastroesophageal junction, GEJ 胃食道接合部(gastroesophageal junction, GEJ)gastroesophageal junction, GEJ(胃食道接合部) が約40 cmを目安にする。体格などで変わるため、内視鏡では実測した距離と解剖学的指標 anatomical landmark 解剖学的指標(anatomical landmark) anatomical landmark(解剖学的指標) を併記する。
層構造
| 層 | 内容 |
|---|---|
| 粘膜 | 重層扁平上皮stratified squamous epithelium重層扁平上皮(stratified squamous epithelium)stratified squamous epithelium(重層扁平上皮) |
| 粘膜下層submucosa粘膜下層(submucosa)submucosa(粘膜下層) | 血管・神経・腺 |
| 固有筋層muscularis propria固有筋層(muscularis propria)muscularis propria(固有筋層) | 内輪inner ring 内輪(inner ring)inner ring(内輪) 走筋と外縦走筋 longitudinal muscle (layer) 縦走筋(longitudinal muscle (layer)) longitudinal muscle (layer)(縦走筋) からなる。上部は横紋筋優位、下部は平滑筋優位 |
| 外膜 | 疎性線維性結合組織 fibrous connective tissue線維性結合組織(fibrous connective tissue) fibrous connective tissue(線維性結合組織)。胸部食道thoracic esophagus 胸部食道(thoracic esophagus)thoracic esophagus(胸部食道) には漿膜がない |
粘膜内の薄い粘膜筋板Muscularis mucosae粘膜筋板(Muscularis mucosae)Muscularis mucosae(粘膜筋板)と、壁の運動を担う固有筋層muscularis propria固有筋層(muscularis propria)muscularis propria(固有筋層)を区別する。深達度depth of invasion 深達度(depth of invasion)depth of invasion(深達度) の評価やEUSでの壁層の判読では、どの層まで病変が達するかが重要になる。
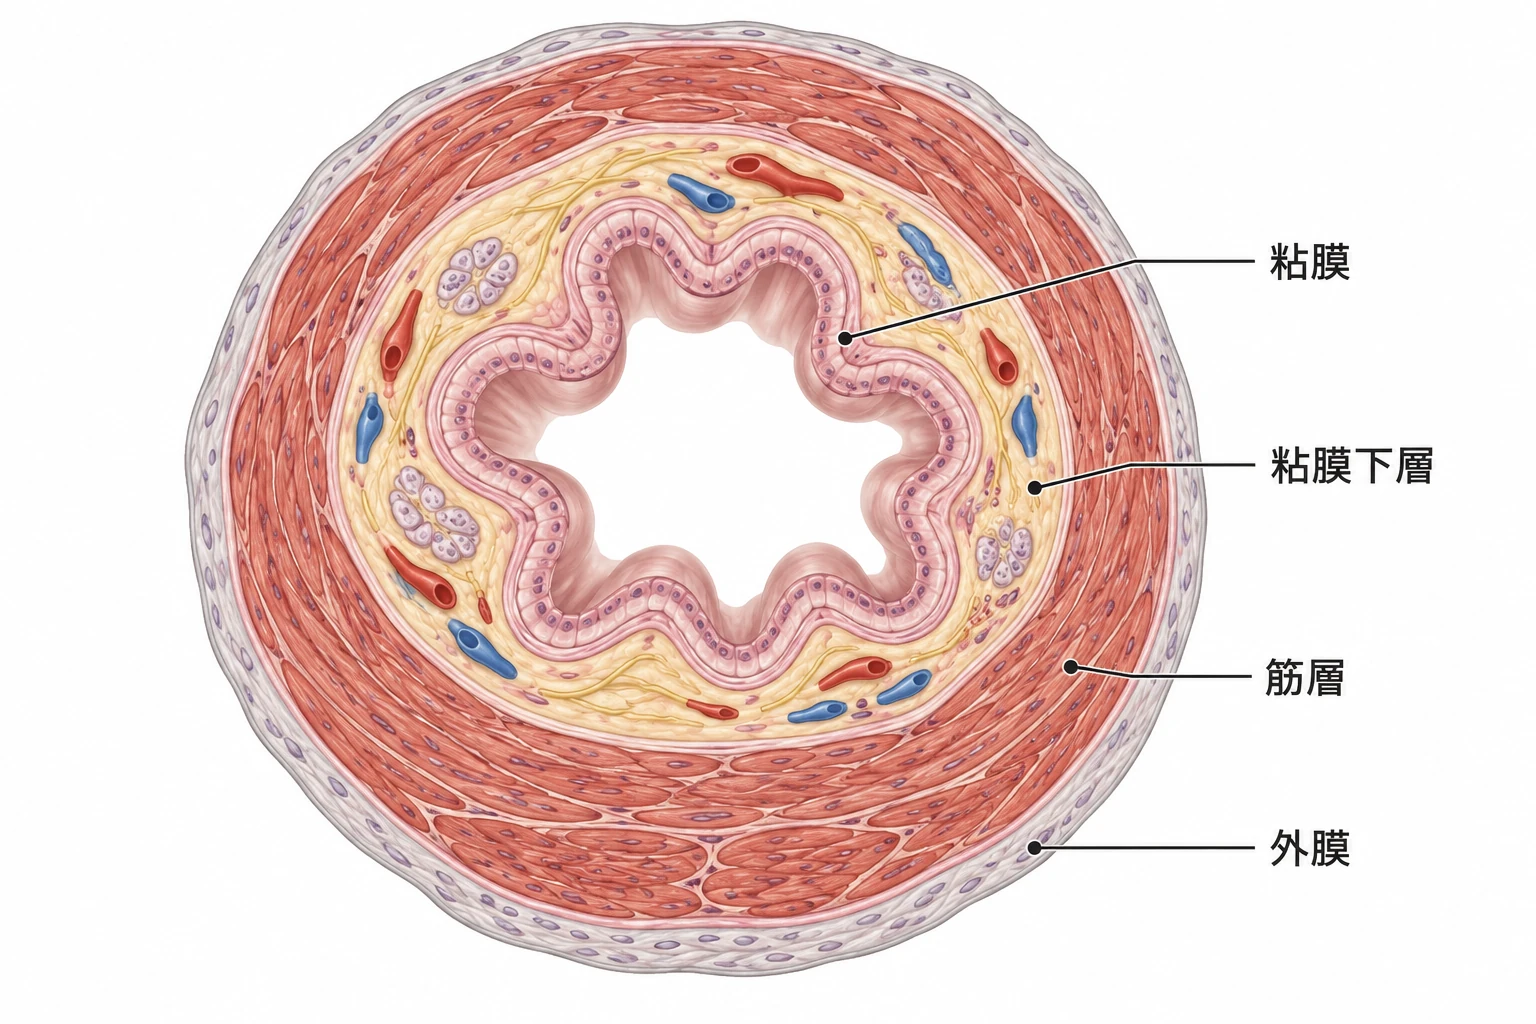
生成模式図(実際の患者画像ではありません)。
血流
| 部位 | 主な動脈供給 | 主な静脈還流 |
|---|---|---|
| 頸部 | 下甲状腺動脈inferior thyroid artery 下甲状腺動脈(inferior thyroid artery)inferior thyroid artery(下甲状腺動脈) の枝 | 下甲状腺静脈 → 腕頭静脈brachiocephalic vein腕頭静脈(brachiocephalic vein)brachiocephalic vein(腕頭静脈) → 上大静脈superior vena cava (SVC)上大静脈(superior vena cava (SVC))superior vena cava (SVC)(上大静脈) |
| 胸部 | 気管支動脈bronchial artery気管支動脈(bronchial artery)bronchial artery(気管支動脈)、胸部大動脈の食道枝など | 奇静脈azygos vein奇静脈(azygos vein)azygos vein(奇静脈)・半奇静脈hemiazygos vein 半奇静脈(hemiazygos vein)hemiazygos vein(半奇静脈) 系 → 上大静脈superior vena cava (SVC)上大静脈(superior vena cava (SVC))superior vena cava (SVC)(上大静脈) |
| 腹部 | 左胃動脈left gastric artery左胃動脈(left gastric artery)left gastric artery(左胃動脈)・下横隔膜動脈の枝 | 左胃静脈left gastric vein左胃静脈(left gastric vein)left gastric vein(左胃静脈) → 門脈系portal system門脈系(portal system)portal system(門脈系)。正常では肝類洞 hepatic sinusoid肝類洞(hepatic sinusoid) hepatic sinusoid(肝類洞) → 肝静脈hepatic vein肝静脈(hepatic vein)hepatic vein(肝静脈) → 下大静脈を経る |
⚠️ 食道下1/3は門脈系 portal system 門脈系(portal system) portal system(門脈系) と大循環系の吻合部位 portosystemic anastomosis吻合部位(portosystemic anastomosis) portosystemic anastomosis(吻合部位)。 門脈圧亢進症portal hypertension門脈圧亢進症(portal hypertension)portal hypertension(門脈圧亢進症)ではこの吻合を介して食道静脈瘤esophageal varices食道静脈瘤(esophageal varices)esophageal varices(食道静脈瘤)が形成される——肝硬変患者の消化管出血の主要な原因。
神経支配
- 迷走神経: 蠕動運動peristalsis蠕動運動(peristalsis)peristalsis(蠕動運動)、腺分泌、壁内intramural 壁内(intramural)intramural(壁内) 神経叢(Auerbach筋層間神経叢Auerbach (myenteric) plexusAuerbach筋層間神経叢(Auerbach (myenteric) plexus)Auerbach (myenteric) plexus(Auerbach筋層間神経叢)・Meissner粘膜下神経叢Meissner (submucosal) plexusMeissner粘膜下神経叢(Meissner (submucosal) plexus)Meissner (submucosal) plexus(Meissner粘膜下神経叢))を支配
- 交感神経幹sympathetic trunk 交感神経幹(sympathetic trunk)sympathetic trunk(交感神経幹) : 血管運動vasomotor 血管運動(vasomotor)vasomotor(血管運動) 性の交感神経支配 sympathetic innervation交感神経支配(sympathetic innervation) sympathetic innervation(交感神経支配)、痛覚
リンパドレナージ
粘膜下層submucosa粘膜下層(submucosa)submucosa(粘膜下層)・筋層の縦走リンパ管網 longitudinal lymphatic network縦走リンパ管網(longitudinal lymphatic network) longitudinal lymphatic network(縦走リンパ管網) → 深頸リンパ節deep cervical lymph nodes深頸リンパ節(deep cervical lymph nodes)deep cervical lymph nodes(深頸リンパ節)、上部/下部縦隔リンパ節 mediastinal lymph nodes縦隔リンパ節(mediastinal lymph nodes) mediastinal lymph nodes(縦隔リンパ節)、腹腔動脈celiac trunk 腹腔動脈(celiac trunk)celiac trunk(腹腔動脈) 周囲リンパ節。長軸方向に連続するため、食道癌esophageal cancer 食道癌(esophageal cancer)esophageal cancer(食道癌) では原発巣 primary tumor 原発巣(primary tumor) primary tumor(原発巣) の近傍だけでなく離れた領域のリンパ節も評価する。
1. 臨床症状の切り口 — 嚥下障害の診かた
- 嚥下困難dysphagia 嚥下困難(dysphagia)dysphagia(嚥下困難) : 嚥下ができない、または通過が障害される状態
- 嚥下痛odynophagia 嚥下痛(odynophagia)odynophagia(嚥下痛) : 嚥下時の疼痛
🧠 「固形物のみか液体も含むか」「進行性か間欠性か」「痛みを伴うか」の3つの軸で鑑別を絞り込む。 この症状ベースの分類は食道疾患クラスター cluster クラスター(cluster) cluster(クラスター) 全体(O/05〜O/09)の共通の地図になる。
| 症状パターン | 代表的原因 |
|---|---|
| ①固形物のみ・進行性 | 消化性狭窄peptic stricture消化性狭窄(peptic stricture)peptic stricture(消化性狭窄)、食道癌esophageal cancer食道癌(esophageal cancer)esophageal cancer(食道癌)、その他の瘢痕性狭窄 cicatricial stenosis瘢痕性狭窄(cicatricial stenosis) cicatricial stenosis(瘢痕性狭窄) |
| ②固形物のみ・間欠性 | 好酸球性食道炎eosinophilic esophagitis, EoE好酸球性食道炎(eosinophilic esophagitis, EoE)eosinophilic esophagitis, EoE(好酸球性食道炎)、食道ウェブesophageal web食道ウェブ(esophageal web)esophageal web(食道ウェブ)・輪状狭窄ring-like stenosis輪状狭窄(ring-like stenosis)ring-like stenosis(輪状狭窄)、心血管系cardiovascular 心血管系(cardiovascular)cardiovascular(心血管系) の異常による圧排 mass effect圧排(mass effect) mass effect(圧排) |
| ③液体・固形物とも | アカラシアachalasiaアカラシア(achalasia)achalasia(アカラシア)、その他の運動障害(食道下部括約筋lower esophageal sphincter 食道下部括約筋(lower esophageal sphincter)lower esophageal sphincter(食道下部括約筋) の過緊張性/痙攣性運動障害、EGJ流出路閉塞EGJ outflow obstructionEGJ流出路閉塞(EGJ outflow obstruction)EGJ outflow obstruction(EGJ流出路閉塞)、無効食道運動ineffective esophageal motility無効食道運動(ineffective esophageal motility)ineffective esophageal motility(無効食道運動))、強皮症、機能性嚥下障害functional dysphagia機能性嚥下障害(functional dysphagia)functional dysphagia(機能性嚥下障害) |
| ④嚥下痛 odynophagia 嚥下痛(odynophagia) odynophagia(嚥下痛) +嚥下困難 dysphagia嚥下困難(dysphagia) dysphagia(嚥下困難) | 感染性食道炎infectious esophagitis 感染性食道炎(infectious esophagitis)infectious esophagitis(感染性食道炎) (HSV、Candida、Mycobacterium)、薬剤性食道炎drug-induced esophagitis 薬剤性食道炎(drug-induced esophagitis)drug-induced esophagitis(薬剤性食道炎) (錠剤tablet 錠剤(tablet)tablet(錠剤) による粘膜障害 mucosal injury粘膜障害(mucosal injury) mucosal injury(粘膜障害))、その他(Crohn病) |
💡 発症時から固形物・液体の両方で困るなら運動障害、固形物から始まって進行するなら器質的狭窄 structural stenosis 器質的狭窄(structural stenosis) structural stenosis(器質的狭窄) を疑う。 ただし高度の狭窄では液体も通らなくなるため、液体の嚥下困難 dysphagia 嚥下困難(dysphagia) dysphagia(嚥下困難) だけで腫瘍や狭窄を除外しない。間欠性でも輪状狭窄 ring-like stenosis 輪状狭窄(ring-like stenosis) ring-like stenosis(輪状狭窄) や好酸球性食道炎 eosinophilic esophagitis, EoE 好酸球性食道炎(eosinophilic esophagitis, EoE) eosinophilic esophagitis, EoE(好酸球性食道炎) があり、症状だけでは確定できない。
短期間の増悪、体重減少、出血・貧血、嚥下痛odynophagia嚥下痛(odynophagia)odynophagia(嚥下痛)、嘔吐、高齢での新規発症は精査を急ぐ手がかりになる。咽喉頭pharynx and larynx 咽喉頭(pharynx and larynx)pharynx and larynx(咽喉頭) の異物感 foreign body sensation 異物感(foreign body sensation) foreign body sensation(異物感) だけの訴えと、実際の食物通過障害 obstruction to passage 通過障害(obstruction to passage) obstruction to passage(通過障害) も区別する。
嚥下障害の検査を組み立てる
上部消化管内視鏡upper gastrointestinal endoscopy 上部消化管内視鏡(upper gastrointestinal endoscopy)upper gastrointestinal endoscopy(上部消化管内視鏡) と必要な生検で、腫瘍・狭窄・粘膜病変を評価する。機械的な原因が見つからず閉塞症状が続く場合は、HRMで食道胃接合部 gastroesophageal junction, GEJ 食道胃接合部(gastroesophageal junction, GEJ) gastroesophageal junction, GEJ(食道胃接合部) の弛緩と体部の収縮を調べる。造影検査とFLIPは、内視鏡や内圧検査だけでは分からない通過・拡張性diastolic 拡張性(diastolic)diastolic(拡張性) を補う。3
flowchart TD
  A["食道性の嚥下障害<br>発症・進行・<span class='jp-term jp-term-diagram' title='warnings'>警告</span>症状・既往を確認"] --> B["内視鏡と必要な生検<br>複雑な狭窄や憩室では造影検査も組み合わせる"]
  B --> C{"<span class='jp-term jp-term-diagram' title='organic (structural, as opposed to functional)'>器質的</span>・粘膜病変があるか"}
  C -->|"ある"| D["腫瘍・狭窄・食道炎などの<span class='jp-term jp-term-diagram' title='Cause-specific treatment'>原因別治療</span>"]
  C -->|"見つからない"| E["HRMで運動障害を評価"]
  E --> F["不確定ならタイムド造影やFLIPで補完"]
F --> G["<span class='jp-term jp-term-diagram' title='organic (structural, as opposed to functional)'>器質的</span>・炎症性・運動性病変を評価したうえで<br>逆流や機能性の病態を検討"]放射線治療、腐食性損傷caustic injury腐食性損傷(caustic injury)caustic injury(腐食性損傷)、食道手術の既往がある複雑な狭窄では、造影で形態を把握 grasp 把握(grasp) grasp(把握) することが内視鏡挿入の安全性にもつながる。CTは外部からの圧排 mass effect 圧排(mass effect) mass effect(圧排) や合併症・腫瘍の広がりの評価に用い、PET-CTを嚥下障害の全例に行うわけではない。
先天性疾患との関係
食道閉鎖esophageal atresia 食道閉鎖(esophageal atresia)esophageal atresia(食道閉鎖) では口側 oral side (proximal, toward the mouth) 口側(oral side (proximal, toward the mouth)) oral side (proximal, toward the mouth)(口側) 食道が盲端 blind end 盲端(blind end) blind end(盲端) となり、肛門側食道が気管と交通する型が多い。瘻を伴わない閉鎖、口側oral side (proximal, toward the mouth) 口側(oral side (proximal, toward the mouth))oral side (proximal, toward the mouth)(口側) の瘻、両側の瘻もあり、食道が連続したまま気管と交通するH型もある。通過路の断絶と気道への交通を分けて考えると、嚥下障害と誤嚥の機序が理解できる。先天性狭窄、喉頭気管食道裂Laryngotracheoesophageal cleft喉頭気管食道裂(Laryngotracheoesophageal cleft)Laryngotracheoesophageal cleft(喉頭気管食道裂)、食道重複嚢胞esophageal duplication cyst 食道重複嚢胞(esophageal duplication cyst)esophageal duplication cyst(食道重複嚢胞) も鑑別に含む。
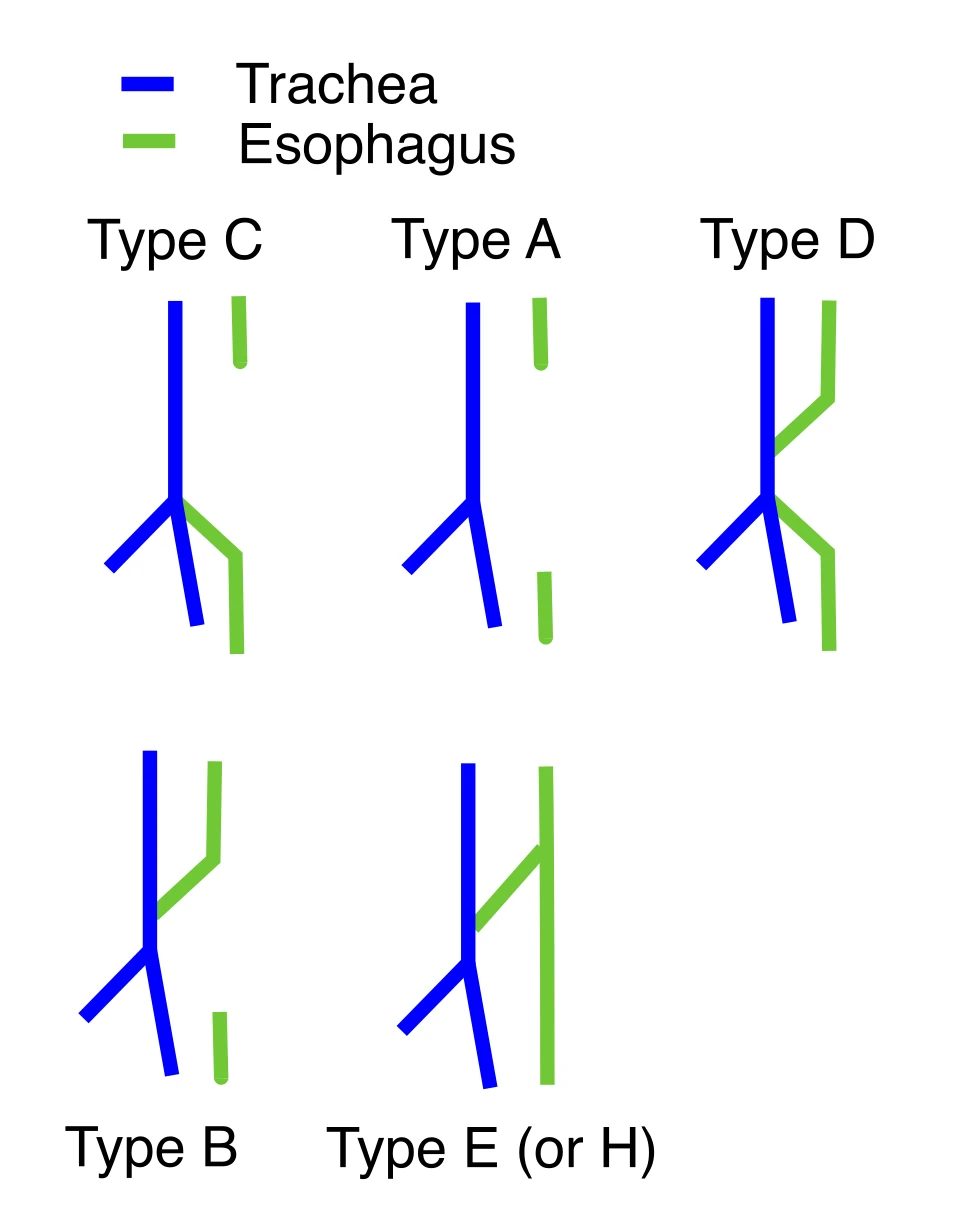
出典:Jmarchn「Tracheoesophageal Fistula Types.svg」(Wikimedia Commons)(CC BY-SA 3.0)。SVGを白背景でWebPに変換、図の内容は変更なし。青は気管、緑は食道。

2. 食道裂孔ヘルニア
定義: 主に胃が横隔膜の食道裂孔 esophageal hiatus 食道裂孔(esophageal hiatus) esophageal hiatus(食道裂孔) を通って胸腔内 intrathoracic 胸腔内(intrathoracic) intrathoracic(胸腔内) へ脱出した状態。
2.1 病因
flowchart TD
  A["素因<br>加齢・喫煙・肥満・<span class='jp-term jp-term-diagram' title='genetic predisposition'>遺伝的素因</span>(稀)"] --> B["<span class='jp-term jp-term-diagram' title='esophageal hiatus'>食道裂孔</span>の弛緩"]
  P["<span class='jp-term jp-term-diagram' title='intra-abdominal pressure'>腹腔内圧</span>の持続的上昇<br>妊娠・腹水・<span class='jp-term jp-term-diagram' title='chronic cough'>慢性咳嗽</span>・慢性便秘"] --> B
  B --> C["相対的な<span class='jp-term jp-term-diagram' title='intrathoracic negative pressure'>胸腔内陰圧</span> + 緩んだ裂孔"]
  C --> D["腹腔内容物の<span class='jp-term jp-term-diagram' title='intrathoracic'>胸腔内</span>への脱出"]
  D --> E["逆流バリアの喪失 + 遠位食道の排出障害"]
E --> F["<span class='jp-term jp-term-diagram' title='gastroesophageal reflux disease, GERD'>胃食道逆流症</span>"]- 加齢 → 横隔食道靱帯phreno-esophageal ligament 横隔食道靱帯(phreno-esophageal ligament)phreno-esophageal ligament(横隔食道靱帯) が脆弱化 detrusor weakness脆弱化(detrusor weakness) detrusor weakness(脆弱化)
- 喫煙 → 横隔膜脚diaphragmatic crura 横隔膜脚(diaphragmatic crura)diaphragmatic crura(横隔膜脚) のエラスチン elastin エラスチン(elastin) elastin(エラスチン) 線維が失われる
- 肥満 → 脚周囲への脂肪沈着 steatosis脂肪沈着(steatosis) steatosis(脂肪沈着) → 裂孔が開大
2.2 分類
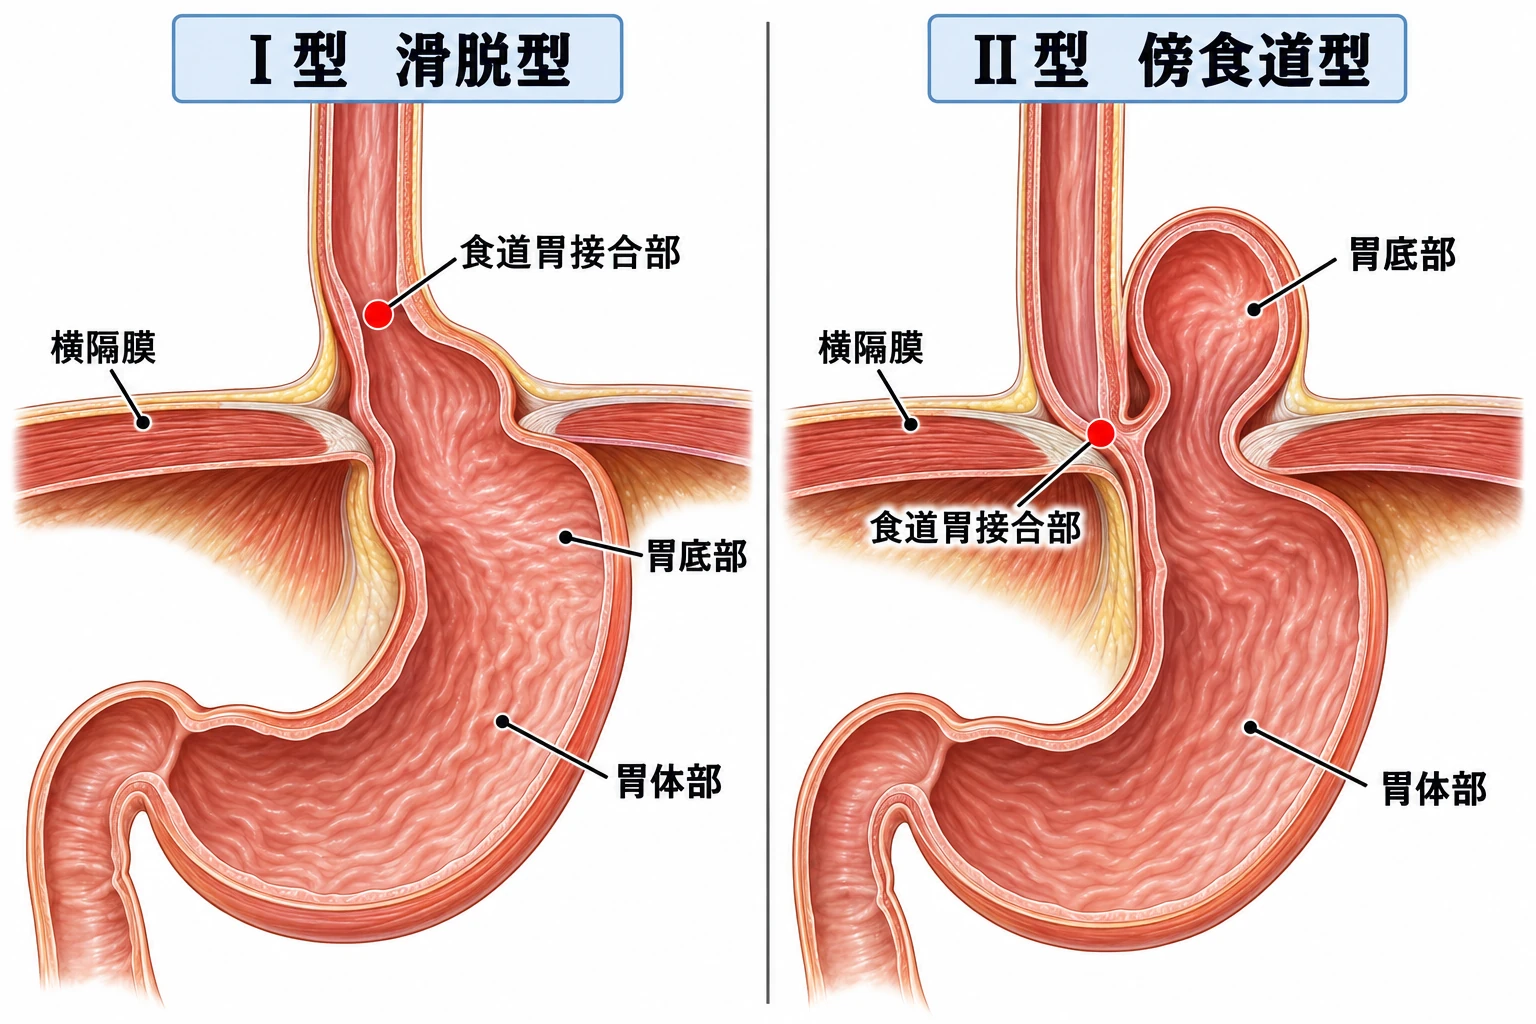
生成模式図(実際の患者画像ではありません)。
現在広く使われているI〜IV型の解剖学的分類は、SAGESの2013年の食道裂孔ヘルニア hiatal hernia 食道裂孔ヘルニア(hiatal hernia) hiatal hernia(食道裂孔ヘルニア) 診療指針に定義がそろっている。II〜IV型をひとまとめに傍食道ヘルニア paraesophageal hernia 傍食道ヘルニア(paraesophageal hernia) paraesophageal hernia(傍食道ヘルニア) と呼び、胃食道接合部gastroesophageal junction, GEJ 胃食道接合部(gastroesophageal junction, GEJ)gastroesophageal junction, GEJ(胃食道接合部) 周囲の後外側の横隔食道靱帯 phreno-esophageal ligament 横隔食道靱帯(phreno-esophageal ligament) phreno-esophageal ligament(横隔食道靱帯) 付着が比較的保たれている点でI型と区別する。4
| 型 | 別名 | 頻度 | 定義 |
|---|---|---|---|
| I型(滑脱型sliding type滑脱型(sliding type)sliding type(滑脱型)) | — | 食道裂孔ヘルニアhiatal hernia 食道裂孔ヘルニア(hiatal hernia)hiatal hernia(食道裂孔ヘルニア) 全体の95%超 | 食道胃接合部gastroesophageal junction, GEJ 食道胃接合部(gastroesophageal junction, GEJ)gastroesophageal junction, GEJ(食道胃接合部) が横隔膜上 epiphrenic 横隔膜上(epiphrenic) epiphrenic(横隔膜上) へ移動する。胃は通常の長軸方向の向きを保ち、胃底部gastric fundus 胃底部(gastric fundus)gastric fundus(胃底部) は食道胃接合部 gastroesophageal junction, GEJ 食道胃接合部(gastroesophageal junction, GEJ) gastroesophageal junction, GEJ(食道胃接合部) より下にとどまる。裂孔で締められた胃が砂時計状 hourglass-shaped 砂時計状(hourglass-shaped) hourglass-shaped(砂時計状) に見えることから砂時計胃 hourglass stomach 砂時計胃(hourglass stomach) hourglass stomach(砂時計胃) とも呼ばれる |
| II型(純粋な傍食道型 Paraesophageal type傍食道型(Paraesophageal type) Paraesophageal type(傍食道型)) | 非滑脱型 sliding type滑脱型(sliding type) sliding type(滑脱型) | 傍食道ヘルニアparaesophageal hernia 傍食道ヘルニア(paraesophageal hernia)paraesophageal hernia(傍食道ヘルニア) のなかで最も少ない | 食道胃接合部gastroesophageal junction, GEJ 食道胃接合部(gastroesophageal junction, GEJ)gastroesophageal junction, GEJ(食道胃接合部) は正常な解剖学的位置にとどまり、胃底部gastric fundus 胃底部(gastric fundus)gastric fundus(胃底部) の一部が食道の傍らを通って裂孔から脱出する |
| III型(混合型) | — | 傍食道ヘルニアparaesophageal hernia 傍食道ヘルニア(paraesophageal hernia)paraesophageal hernia(傍食道ヘルニア) の90%超 | I型とII型の混合で、食道胃接合部gastroesophageal junction, GEJ 食道胃接合部(gastroesophageal junction, GEJ)gastroesophageal junction, GEJ(食道胃接合部) と胃底部 gastric fundus 胃底部(gastric fundus) gastric fundus(胃底部) がともに脱出する。胃底部gastric fundus 胃底部(gastric fundus)gastric fundus(胃底部) は食道胃接合部 gastroesophageal junction, GEJ 食道胃接合部(gastroesophageal junction, GEJ) gastroesophageal junction, GEJ(食道胃接合部) より上に位置する |
| IV型 | — | 稀 | 胃以外の構造物(大網greater omentum大網(greater omentum)greater omentum(大網)・結腸・小腸など)がヘルニア嚢 hernial sac ヘルニア嚢(hernial sac) hernial sac(ヘルニア嚢) 内にあるもの。裂孔の欠損が大きいことを反映する |
⚠️ IV型を「胃全体が胸に入ったもの」と覚えない。 IV型を定義するのは脱出した胃の量ではなく、胃以外の臓器がヘルニア嚢 hernial sac ヘルニア嚢(hernial sac) hernial sac(ヘルニア嚢) に入っていることである。胃の大半が胸腔内 intrathoracic 胸腔内(intrathoracic) intrathoracic(胸腔内) にあり反転したもの(逆位胃upside-down stomach逆位胃(upside-down stomach)upside-down stomach(逆位胃))は臨床では「巨大傍食道ヘルニアgiant paraesophageal hernia巨大傍食道ヘルニア(giant paraesophageal hernia)giant paraesophageal hernia(巨大傍食道ヘルニア)」と呼ばれるが、この語の定義は資料によって一定せず、多くは胃の1/3〜1/2を超える部分が胸腔内 intrathoracic 胸腔内(intrathoracic) intrathoracic(胸腔内) にあるものを指す。4
- I型 の症状: 逆流性regurgitant 逆流性(regurgitant)regurgitant(逆流性) の胸やけ heartburn胸やけ(heartburn) heartburn(胸やけ)、仰臥位で増悪、酸性の逆流。GERDに直結しやすい
- II〜IV型 の症状: しゃっくりhiccupsしゃっくり(hiccups)hiccups(しゃっくり)、胸部圧迫感chest tightness胸部圧迫感(chest tightness)chest tightness(胸部圧迫感)、嚥下痛odynophagia嚥下痛(odynophagia)odynophagia(嚥下痛)、呼吸困難、心窩部epigastrium心窩部(epigastrium)epigastrium(心窩部)・胸骨下の痛み、早期満腹感early satiety早期満腹感(early satiety)early satiety(早期満腹感)、えづき
⚠️ II〜IV型は嵌頓して閉塞や胃軸捻転 gastric volvulus 胃軸捻転(gastric volvulus) gastric volvulus(胃軸捻転) を起こしうる。無症候の傍食道ヘルニア paraesophageal hernia 傍食道ヘルニア(paraesophageal hernia) paraesophageal hernia(傍食道ヘルニア) が急性症状 acute symptoms 急性症状(acute symptoms) acute symptoms(急性症状) を起こして緊急手術に至る確率は年間およそ1%と推計されており、待機手術elective surgery 待機手術(elective surgery)elective surgery(待機手術) の可否はこの低い年間リスクと手術リスク surgical risk 手術リスク(surgical risk) surgical risk(手術リスク) の比較になる。2
2.3 臨床像
- 多くは無症状
- 慢性逆流 → 慢性炎症 → 粘膜変性 → 線維化・瘢痕化scarring瘢痕化(scarring)scarring(瘢痕化) → 狭窄・嚥下障害。慢性逆流では別の経路としてバレット食道Barrett esophagus バレット食道(Barrett esophagus)Barrett esophagus(バレット食道) の腸上皮化生 intestinal metaplasia 腸上皮化生(intestinal metaplasia) intestinal metaplasia(腸上皮化生) →腺癌も問題になる。瘢痕性狭窄cicatricial stenosis 瘢痕性狭窄(cicatricial stenosis)cicatricial stenosis(瘢痕性狭窄) そのものをバレット食道 Barrett esophagus バレット食道(Barrett esophagus) Barrett esophagus(バレット食道) の前駆段階と考えない
2.4 診断
| 検査 | 内容 |
|---|---|
| バリウム嚥下barium swallowバリウム嚥下(barium swallow)barium swallow(バリウム嚥下) | 造影剤を嚥下しながら胸部X線を撮影。狭窄・輪状狭窄ring-like stenosis輪状狭窄(ring-like stenosis)ring-like stenosis(輪状狭窄)・拡張などの解剖学的異常を同定 |
| 内視鏡 | 胃食道接合部gastroesophageal junction, GEJ胃食道接合部(gastroesophageal junction, GEJ)gastroesophageal junction, GEJ(胃食道接合部)、横隔膜による締め付け、扁平円柱上皮接合部squamocolumnar junction (Z-line) 扁平円柱上皮接合部(squamocolumnar junction (Z-line))squamocolumnar junction (Z-line)(扁平円柱上皮接合部) を別々に確認する。粘膜病変・バレット食道Barrett esophagus バレット食道(Barrett esophagus)Barrett esophagus(バレット食道) も評価し、型分類は造影などと合わせて判断する5 |
| 食道内圧検査esophageal manometry食道内圧検査(esophageal manometry)esophageal manometry(食道内圧検査) | LESと横隔膜脚 diaphragmatic crura 横隔膜脚(diaphragmatic crura) diaphragmatic crura(横隔膜脚) がつくる高圧帯の分離を評価する。抗逆流治療の前には運動障害の除外が重要 |
| CT | 複雑なII〜IV型ヘルニアの緊急術前評価に推奨 |
| 胸部X線 | 偶発的発見incidental finding偶発的発見(incidental finding)incidental finding(偶発的発見) |
💡 胃食道接合部gastroesophageal junction, GEJ 胃食道接合部(gastroesophageal junction, GEJ)gastroesophageal junction, GEJ(胃食道接合部) と扁平円柱上皮接合部 squamocolumnar junction (Z-line) 扁平円柱上皮接合部(squamocolumnar junction (Z-line)) squamocolumnar junction (Z-line)(扁平円柱上皮接合部) は、同じものではない。 前者は食道と胃の解剖学的境界、後者は上皮の種類が切り替わる粘膜の境界である。バレット食道Barrett esophagus バレット食道(Barrett esophagus)Barrett esophagus(バレット食道) では円柱上皮が食道側へ広がるため、上皮の境界だけを胃の位置の目印にすると誤る。内視鏡では胃粘膜 gastric mucosa 胃粘膜(gastric mucosa) gastric mucosa(胃粘膜) ひだの口側 oral side (proximal, toward the mouth) 口側(oral side (proximal, toward the mouth)) oral side (proximal, toward the mouth)(口側) 端などを胃食道接合部 gastroesophageal junction, GEJ 胃食道接合部(gastroesophageal junction, GEJ) gastroesophageal junction, GEJ(胃食道接合部) の目安とし、横隔膜の締め付け位置との関係を記録する。5
I型・III型は胃食道接合部gastroesophageal junction, GEJ 胃食道接合部(gastroesophageal junction, GEJ)gastroesophageal junction, GEJ(胃食道接合部) そのものが挙上し、II型は接合部が本来の位置に保たれたまま胃底部 gastric fundus 胃底部(gastric fundus) gastric fundus(胃底部) が脱出する。IV型は胃以外の臓器の脱出で定義されるため、上皮の境界の位置だけでは判定できない。4
2.5 治療
| 病型・症状 | 方針 |
|---|---|
| 無症状の滑脱型 sliding type 滑脱型(sliding type) sliding type(滑脱型) ヘルニア | 経過観察のみ |
| 症状のある滑脱型 sliding type 滑脱型(sliding type) sliding type(滑脱型) ヘルニア | GERDに準じた内科的治療 |
| 無症候〜軽症のII〜IV型 | 手術か経過観察かで判断が分かれる。下の⭐を参照 |
| 症状のあるII〜IV型 | 待機的elective 待機的(elective)elective(待機的) または緊急手術(胃軸捻転gastric volvulus胃軸捻転(gastric volvulus)gastric volvulus(胃軸捻転)、制御不能出血、閉塞、絞扼、穿孔、呼吸障害respiratory impairment 呼吸障害(respiratory impairment)respiratory impairment(呼吸障害) がある場合) |
⭐ 無症候〜軽症の傍食道ヘルニア paraesophageal hernia 傍食道ヘルニア(paraesophageal hernia) paraesophageal hernia(傍食道ヘルニア) をどうするか。 EAESの2023年の迅速ガイドラインは、胃の50%超が胸腔内 intrathoracic 胸腔内(intrathoracic) intrathoracic(胸腔内) へ脱出した中等度〜大型のII〜IV型を対象に、次の2つを別々の推奨として置いている。向きも強さも違うので、片方だけを覚えない。2
対象 推奨 強さ 無症候〜軽症の傍食道ヘルニア paraesophageal hernia 傍食道ヘルニア(paraesophageal hernia) paraesophageal hernia(傍食道ヘルニア) (一般) 保存的管理conservative management 保存的管理(conservative management)conservative management(保存的管理) より手術を提案する 条件付き推奨 同じ病態でも虚弱な患者 手術より保存的管理 conservative management 保存的管理(conservative management) conservative management(保存的管理) を推奨する 強い推奨 ⚠️ この文書のエビデンスの確実性はどの転帰でも非常に低く、パネル自身が「無症候・軽症例を保存的に管理してきた外科医には診療の変更を求める内容である」と書いている。虚弱な患者についてだけ強い推奨が付いていることが、この指針のいちばん重い部分である。傍食道ヘルニアparaesophageal hernia 傍食道ヘルニア(paraesophageal hernia)paraesophageal hernia(傍食道ヘルニア) の診断年齢の中央値は65〜75歳で、高齢者ほど併存疾患 comorbidity併存疾患(comorbidity) comorbidity(併存疾患)・体力低下・虚弱を伴い手術リスク surgical risk 手術リスク(surgical risk) surgical risk(手術リスク) が上がる。2
SAGES 2024は、II〜IV型の真に無症候な患者に対する根拠が不足しているとし、貧血・呼吸困難・客観的objective 客観的(objective)objective(客観的) 逆流・微小誤嚥microaspiration 微小誤嚥(microaspiration)microaspiration(微小誤嚥) なども確認したうえで、手術と経過観察を話し合う。精査で異常がなく、胃軸捻転gastric volvulus 胃軸捻転(gastric volvulus)gastric volvulus(胃軸捻転) などのリスクを理解して受け入れる場合は経過観察も妥当とする。EAES 2023の対象・条件付き推奨と、SAGESの専門家意見 expert opinion 専門家意見(expert opinion) expert opinion(専門家意見) を区別する。6
保存的治療:
- 生活習慣Lifestyle 生活習慣(Lifestyle)Lifestyle(生活習慣) の是正(減量、食事内容の変更、禁煙)
- 薬物療法(PPIによる逆流症状の管理)
手術:
-
経腹的修復transabdominal repair 経腹的修復(transabdominal repair)transabdominal repair(経腹的修復) (開腹/腹腔鏡)
- 噴門形成術fundoplication噴門形成術(fundoplication)fundoplication(噴門形成術): 胃底部gastric fundus 胃底部(gastric fundus)gastric fundus(胃底部) で下部食道を包んで抗逆流バリアを補う。Nissen法Nissen fundoplication Nissen法(Nissen fundoplication)Nissen fundoplication(Nissen法) は360度、Toupet法Toupet fundoplication Toupet法(Toupet fundoplication)Toupet fundoplication(Toupet法) は後方部分、Dor法Dor fundoplication Dor法(Dor fundoplication)Dor fundoplication(Dor法) は前方部分の形成である。Hill法Hill repair Hill法(Hill repair)Hill repair(Hill法) は後方固定 posterior fusion 後方固定(posterior fusion) posterior fusion(後方固定) を主体とする別の抗逆流術式
- 胃固定術gastropexy胃固定術(gastropexy)gastropexy(胃固定術): 胃を正常位置に戻し腹壁前面に縫合固定
- 裂孔・ヘルニア嚢hernial sac ヘルニア嚢(hernial sac)hernial sac(ヘルニア嚢) の剥離、食道の授動 mobilization (surgical)授動(mobilization (surgical)) mobilization (surgical)(授動)、裂孔欠損の閉鎖
- ⭐ 噴門形成術fundoplication 噴門形成術(fundoplication)fundoplication(噴門形成術) と胃固定術 gastropexy 胃固定術(gastropexy) gastropexy(胃固定術) の使い分けには向きがある。 EAES 2023は待機的 elective 待機的(elective) elective(待機的) な傍食道ヘルニア paraesophageal hernia 傍食道ヘルニア(paraesophageal hernia) paraesophageal hernia(傍食道ヘルニア) 修復では胃固定術 gastropexy 胃固定術(gastropexy) gastropexy(胃固定術) より噴門形成術fundoplication噴門形成術(fundoplication)fundoplication(噴門形成術)を、心肺機能が不安定で緊急修復を要する患者では逆に噴門形成術 fundoplication 噴門形成術(fundoplication) fundoplication(噴門形成術) より胃固定術gastropexy胃固定術(gastropexy)gastropexy(胃固定術)を提案している(いずれも条件付き推奨)。裂孔の閉鎖については単純縫合 herniorrhaphy 単純縫合(herniorrhaphy) herniorrhaphy(単純縫合) よりメッシュを提案している(条件付き推奨)。2
-
経胸的修復transthoracic repair 経胸的修復(transthoracic repair)transthoracic repair(経胸的修復) (Belsey Mark IV法Belsey Mark IV repairBelsey Mark IV法(Belsey Mark IV repair)Belsey Mark IV repair(Belsey Mark IV法)): 食道短縮、非常に大きい・複雑なヘルニア、再手術revision surgery 再手術(revision surgery)revision surgery(再手術) などで検討される選択肢。肥満だけで経胸的修復 transthoracic repair 経胸的修復(transthoracic repair) transthoracic repair(経胸的修復) を必須とせず、術式と全身状態を総合して決める
SAGES 2024はII〜IV型修復への噴門 cardia 噴門(cardia) cardia(噴門) 形成併施 concomitant (performed together) 併施(concomitant (performed together)) concomitant (performed together)(併施) を条件付きで提案する一方、メッシュの一律使用には賛否の推奨を出していない。裂孔閉鎖closure of the retinal break裂孔閉鎖(closure of the retinal break)closure of the retinal break(裂孔閉鎖)、逆流抑制、胃の再脱出防止を別々の目的として整理する。6
合併症: 上部消化管出血upper gastrointestinal bleeding 上部消化管出血(upper gastrointestinal bleeding)upper gastrointestinal bleeding(上部消化管出血) (潜在性latent潜在性(latent)latent(潜在性)/大量)→鉄欠乏性貧血 iron-deficiency anemia, IDA鉄欠乏性貧血(iron-deficiency anemia, IDA) iron-deficiency anemia, IDA(鉄欠乏性貧血)、胃潰瘍gastric ulcer胃潰瘍(gastric ulcer)gastric ulcer(胃潰瘍)、穿孔、胃軸捻転gastric volvulus胃軸捻転(gastric volvulus)gastric volvulus(胃軸捻転)、完全胃閉塞
3. GERD
- 胃食道逆流gastroesophageal reflux, GER胃食道逆流(gastroesophageal reflux, GER)gastroesophageal reflux, GER(胃食道逆流): 胃内容物の食道への逆流
- GERD: 逆流が症状(胸やけheartburn胸やけ(heartburn)heartburn(胸やけ)、逆流感、嚥下障害)および/または食道傷害・合併症を引き起こす状態
3.1 病因
| 因子 | 内容 |
|---|---|
| 下部食道括約筋lower esophageal sphincter, LES 下部食道括約筋(lower esophageal sphincter, LES)lower esophageal sphincter, LES(下部食道括約筋) 機能異常 | 安静時のLES緊張を下げる要因としてアルコール・薬剤・喫煙・既往手術がある。ただし現在の理解では、緊張低下そのものより一過性LES弛緩transient lower esophageal sphincter relaxation一過性LES弛緩(transient lower esophageal sphincter relaxation)transient lower esophageal sphincter relaxation(一過性LES弛緩)が主要機序で、とくに食道裂孔ヘルニア hiatal hernia 食道裂孔ヘルニア(hiatal hernia) hiatal hernia(食道裂孔ヘルニア) を伴わない患者で重要 |
| 胃内圧intragastric pressure 胃内圧(intragastric pressure)intragastric pressure(胃内圧) 上昇 | 肥満、咳嗽、妊娠、胃排出遅延delayed gastric emptying胃排出遅延(delayed gastric emptying)delayed gastric emptying(胃排出遅延)、歌手・アスリート |
| 酸分泌acid secretion 酸分泌(acid secretion)acid secretion(酸分泌) と逆流内容 | 高ガストリン血症hypergastrinemia 高ガストリン血症(hypergastrinemia)hypergastrinemia(高ガストリン血症) などによる酸分泌 acid secretion 酸分泌(acid secretion) acid secretion(酸分泌) 亢進、逆流内容の性状(酸・胆汁)。ただしGERDの中核は酸が「多い」ことではなく、逆流を止める機構が壊れていること |
| 食道クリアランスesophageal clearance 食道クリアランス(esophageal clearance)esophageal clearance(食道クリアランス) 低下 | 逆流した内容を食道が押し戻す蠕動と唾液による中和が落ちると、粘膜の曝露時間が延びる |
| 食道裂孔ヘルニアhiatal hernia食道裂孔ヘルニア(hiatal hernia)hiatal hernia(食道裂孔ヘルニア) | 噴門cardia 噴門(cardia)cardia(噴門) または胃底部 gastric fundus 胃底部(gastric fundus) gastric fundus(胃底部) が横隔膜を越えて挙上(本ノートの「2. 食道裂孔ヘルニアhiatal hernia食道裂孔ヘルニア(hiatal hernia)hiatal hernia(食道裂孔ヘルニア)」を参照) |
💡 H. pyloriを「酸が絡む病気の共通因子」としてGERDに当てはめない。 H. pylori は消化性潰瘍・胃癌では主役だが、GERDで最初に考えるのは抗逆流バリアの障害・一過性LES弛緩transient lower esophageal sphincter relaxation一過性LES弛緩(transient lower esophageal sphincter relaxation)transient lower esophageal sphincter relaxation(一過性LES弛緩)・食道クリアランスesophageal clearance 食道クリアランス(esophageal clearance)esophageal clearance(食道クリアランス) 低下・食道裂孔ヘルニアhiatal hernia 食道裂孔ヘルニア(hiatal hernia)hiatal hernia(食道裂孔ヘルニア) の有無である。
3.2 臨床像
- 胸やけheartburn胸やけ(heartburn)heartburn(胸やけ)・逆流感が代表的。胸骨後retrosternal 胸骨後(retrosternal)retrosternal(胸骨後) 痛を伴うこともあるが、胸痛では心疾患などの緊急病態を先に評価する
- 夜間、大食後、仰臥位で増悪
- 潰瘍や狭窄を合併すると嚥下障害が出現
3.3 診断
- 内視鏡(発赤、びらん、潰瘍、消化性狭窄peptic stricture消化性狭窄(peptic stricture)peptic stricture(消化性狭窄))。嚥下障害、出血、貧血、体重減少、反復嘔吐recurrent vomiting 反復嘔吐(recurrent vomiting)recurrent vomiting(反復嘔吐) などの警告 warnings 警告(warnings) warnings(警告) 症状があれば内視鏡を優先する。びらん性食道炎erosive esophagitis びらん性食道炎(erosive esophagitis)erosive esophagitis(びらん性食道炎) の重症度はLos Angeles分類Los Angeles classificationLos Angeles分類(Los Angeles classification)Los Angeles classification(Los Angeles分類)(LA分類Los Angeles classificationLA分類(Los Angeles classification)Los Angeles classification(LA分類))A〜Dで記載し、C・Dが「高度逆流性食道炎 reflux esophagitis逆流性食道炎(reflux esophagitis) reflux esophagitis(逆流性食道炎)」にあたる
- 外来逆流モニタリング(24時間pHモニタリング24-hour pH monitoring24時間pHモニタリング(24-hour pH monitoring)24-hour pH monitoring(24時間pHモニタリング)・pHインピーダンス検査 impedance testingインピーダンス検査(impedance testing) impedance testing(インピーダンス検査)):食道への異常逆流を客観化する。診断が不明確で内視鏡が正常な例ではPPIを中止した状態で検査し、すでに確立したGERDで治療抵抗性の例ではPPI内服下のpHインピーダンス検査 impedance testingインピーダンス検査(impedance testing) impedance testing(インピーダンス検査)を選択する
- 食道バリウム嚥下 barium swallowバリウム嚥下(barium swallow) barium swallow(バリウム嚥下)
- 食道内圧検査esophageal manometry食道内圧検査(esophageal manometry)esophageal manometry(食道内圧検査)
| 臨床状況clinical setting臨床状況(clinical setting)clinical setting(臨床状況) | 診断・評価の進め方 |
|---|---|
| 典型症状のみで警告 warnings 警告(warnings) warnings(警告) 症状なし | 生活習慣Lifestyle 生活習慣(Lifestyle)Lifestyle(生活習慣) の調整とPPI試験治療 |
| 診断が不明確・内視鏡で異常なし | PPIを中止した外来逆流モニタリングで逆流を客観化 |
| 確立したGERDでPPI治療抵抗性 | PPI内服下のpHインピーダンス検査 impedance testing インピーダンス検査(impedance testing) impedance testing(インピーダンス検査) を選択 |
| 抗逆流手術antireflux surgery 抗逆流手術(antireflux surgery)antireflux surgery(抗逆流手術) の術前評価 | 上部消化管内視鏡upper gastrointestinal endoscopy上部消化管内視鏡(upper gastrointestinal endoscopy)upper gastrointestinal endoscopy(上部消化管内視鏡)、逆流の客観的 objective 客観的(objective) objective(客観的) 証明、高解像度食道内圧検査high-resolution esophageal manometry 高解像度食道内圧検査(high-resolution esophageal manometry)high-resolution esophageal manometry(高解像度食道内圧検査) を揃える |
3.4 治療
内科的治療:
- 逆流減少 → 禁煙、過体重Overweight 過体重(Overweight)Overweight(過体重) なら減量、節酒reduced alcohol intake節酒(reduced alcohol intake)reduced alcohol intake(節酒)、就寝前2〜3時間の食事回避、夜間症状がある例でのベッド頭側挙上 head-of-bed elevation頭側挙上(head-of-bed elevation) head-of-bed elevation(頭側挙上)、個々に症状を再現する誘因食品の回避
- 酸分泌抑制 → PPI((エス)オメプラゾール(es)omeprazole(エス)オメプラゾール((es)omeprazole)(es)omeprazole((エス)オメプラゾール)など、食前に適切に服用する)が中心。H2受容体拮抗薬H2 receptor antagonist H2受容体拮抗薬(H2 receptor antagonist)H2 receptor antagonist(H2受容体拮抗薬) は軽症例や夜間症状の選択肢、制酸薬antacids 制酸薬(antacids)antacids(制酸薬) は対症的に用いる
- 消化管運動亢進increased gastrointestinal motility 消化管運動亢進(increased gastrointestinal motility)increased gastrointestinal motility(消化管運動亢進) 薬はGERDの全例に用いず、胃不全麻痺gastroparesis 胃不全麻痺(gastroparesis)gastroparesis(胃不全麻痺) などの合併病態を評価して検討する1
外科的治療endovascular/surgical intervention外科的治療(endovascular/surgical intervention)endovascular/surgical intervention(外科的治療):
- 腹腔鏡下噴門形成術laparoscopic fundoplication腹腔鏡下噴門形成術(laparoscopic fundoplication)laparoscopic fundoplication(腹腔鏡下噴門形成術): 胃底部gastric fundus 胃底部(gastric fundus)gastric fundus(胃底部) を腹腔内食道に巻き付けて縫合しカフを形成 → 遠位食道と食道胃接合部 gastroesophageal junction, GEJ 食道胃接合部(gastroesophageal junction, GEJ) gastroesophageal junction, GEJ(食道胃接合部) を狭小化し逆流を防止。全周性circumferential 全周性(circumferential)circumferential(全周性) のNissen法 Nissen fundoplication Nissen法(Nissen fundoplication) Nissen fundoplication(Nissen法) (360度)と部分噴門形成術 partial fundoplication 部分噴門形成術(partial fundoplication) partial fundoplication(部分噴門形成術) (後方Toupet法 Toupet fundoplicationToupet法(Toupet fundoplication) Toupet fundoplication(Toupet法)・前方Dor法 Dor fundoplicationDor法(Dor fundoplication) Dor fundoplication(Dor法))は、食道運動esophageal motility 食道運動(esophageal motility)esophageal motility(食道運動) 機能と術後嚥下障害のリスクを踏まえて選ぶ。なお、慢性GERD 554例(欧州11か国)を対象とした5年間の無作為化比較試験 randomized controlled trial (RCT) 無作為化比較試験(randomized controlled trial (RCT)) randomized controlled trial (RCT)(無作為化比較試験) (LOTUS試験)では、腹腔鏡下噴門形成術laparoscopic fundoplication 腹腔鏡下噴門形成術(laparoscopic fundoplication)laparoscopic fundoplication(腹腔鏡下噴門形成術) とエソメプラゾール (es)omeprazole エソメプラゾール((es)omeprazole) (es)omeprazole(エソメプラゾール) 継続投与のいずれも5年時点で大半の患者が寛解を維持しており(推定寛解率:エソメプラゾール (es)omeprazole エソメプラゾール((es)omeprazole) (es)omeprazole(エソメプラゾール) 群92%、噴門形成術fundoplication 噴門形成術(fundoplication)fundoplication(噴門形成術) 群85%)、「手術の方が内科治療より明確に優れる」とは単純化せず、客観的objective 客観的(objective)objective(客観的) 逆流の証明・大きな裂孔ヘルニア hiatal hernia裂孔ヘルニア(hiatal hernia) hiatal hernia(裂孔ヘルニア)・薬物不耐性・長期治療の希望などを踏まえて選択する7
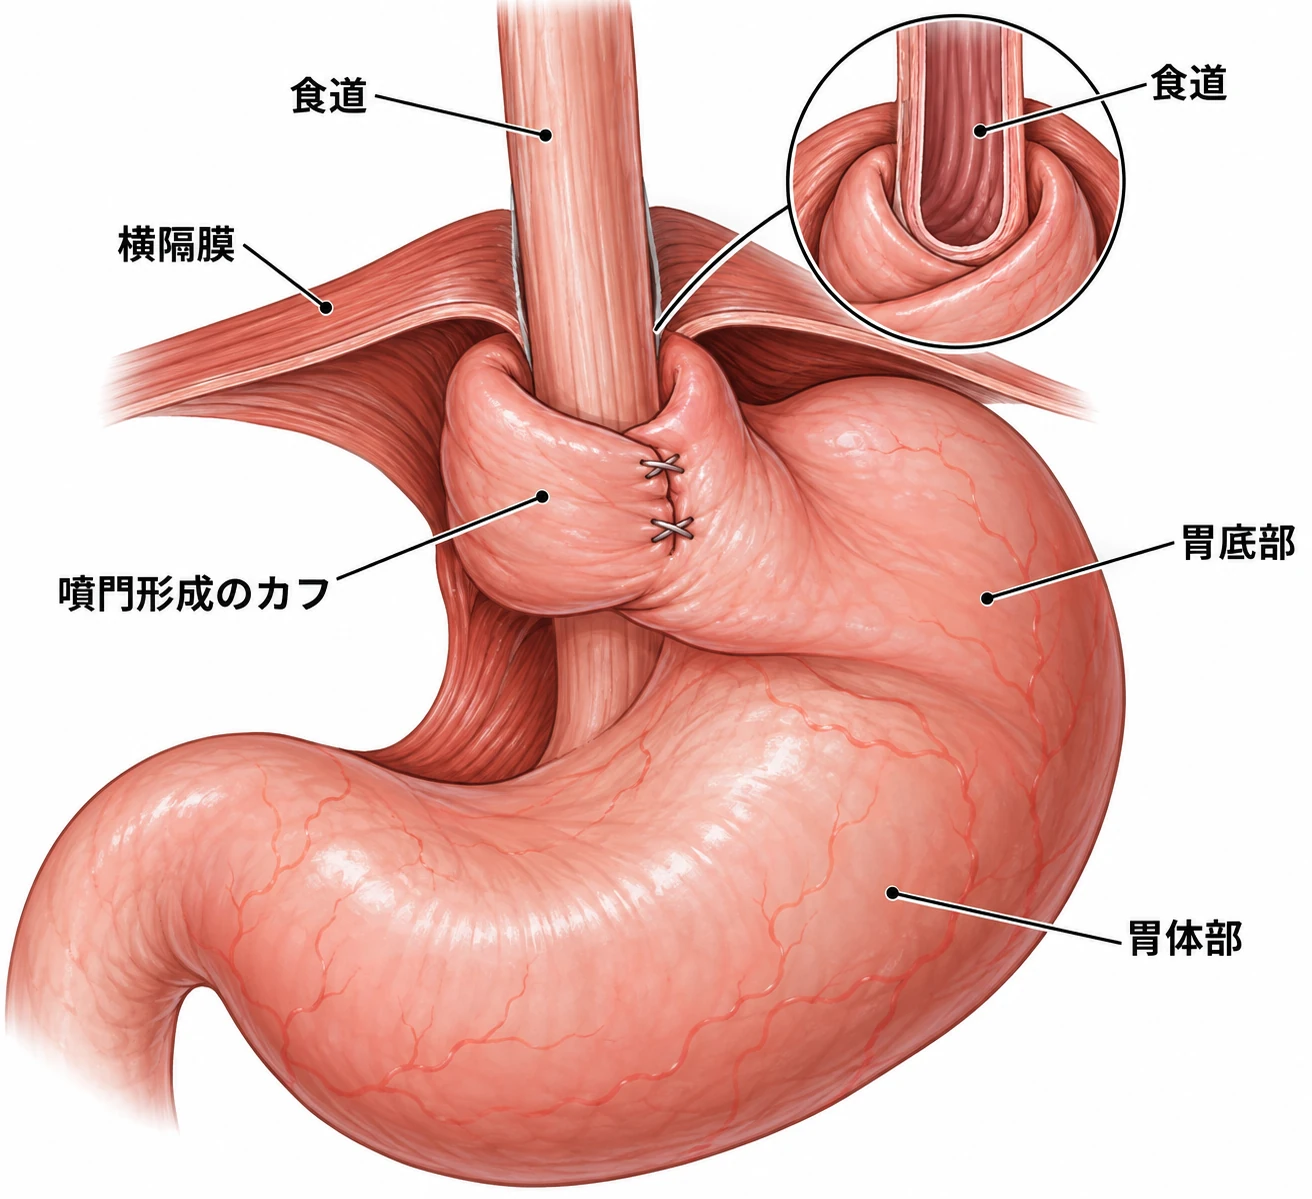
生成模式図(実際の患者画像ではありません)。
古典的に外科側で挙げられてきた手術適応は次の6つである。
- 内科的治療で制御できない
- 内科的治療を継続できない(服薬アドヒアランス不良poor medication adherence服薬アドヒアランス不良(poor medication adherence)poor medication adherence(服薬アドヒアランス不良))
- 逆流量regurgitant volume 逆流量(regurgitant volume)regurgitant volume(逆流量) が多い
- 内視鏡で高度の食道炎がある
- 良性狭窄がある
- 円柱上皮化生intestinal metaplasia 円柱上皮化生(intestinal metaplasia)intestinal metaplasia(円柱上皮化生) (バレットBarrett バレット(Barrett)Barrett(バレット) 上皮)があり、高度異形成high-grade dysplasia高度異形成(high-grade dysplasia)high-grade dysplasia(高度異形成)・癌を伴わない
⚠️ 6番目の扱いだけは現在の指針と読み方が違う。 下で見るように、ACGのバレット食道 Barrett esophagus バレット食道(Barrett esophagus) Barrett esophagus(バレット食道) ガイドラインは癌化予防を目的とした抗逆流手術 antireflux surgery抗逆流手術(antireflux surgery) antireflux surgery(抗逆流手術)を提案しない立場である。バレット食道Barrett esophagus バレット食道(Barrett esophagus)Barrett esophagus(バレット食道) があること自体を手術の理由にはせず、逆流をどれだけ制御できていないかで判断する。
ACG 2022年のGERD診療ガイドラインは、客観的objective 客観的(objective)objective(客観的) な逆流の証拠がある患者に対し、経験豊富な外科医が行う抗逆流手術 antireflux surgery 抗逆流手術(antireflux surgery) antireflux surgery(抗逆流手術) を長期治療の選択肢として推奨する(強い推奨、エビデンスの質は中等度)。とくに恩恵が大きいのは高度逆流性食道炎 reflux esophagitis 逆流性食道炎(reflux esophagitis) reflux esophagitis(逆流性食道炎) (LA分類Los Angeles classificationLA分類(Los Angeles classification)Los Angeles classification(LA分類) C・D)、大きな食道裂孔ヘルニア hiatal hernia食道裂孔ヘルニア(hiatal hernia) hiatal hernia(食道裂孔ヘルニア)、内科治療でも残る煩わしい逆流症状をもつ患者である。LA C・Dの食道炎では「PPIの維持投与 maintenance dosing 維持投与(maintenance dosing) maintenance dosing(維持投与) を無期限に続ける か 抗逆流手術antireflux surgery抗逆流手術(antireflux surgery)antireflux surgery(抗逆流手術)」が同じ強さで並べられている。1
⚠️ 手術の前に高解像度食道内圧検査 high-resolution esophageal manometry 高解像度食道内圧検査(high-resolution esophageal manometry) high-resolution esophageal manometry(高解像度食道内圧検査) を行う。 同ガイドラインは抗逆流手術 antireflux surgery抗逆流手術(antireflux surgery) antireflux surgery(抗逆流手術)・内視鏡治療endoscopic treatment 内視鏡治療(endoscopic treatment)endoscopic treatment(内視鏡治療) に先立って高解像度食道内圧検査high-resolution esophageal manometry高解像度食道内圧検査(high-resolution esophageal manometry)high-resolution esophageal manometry(高解像度食道内圧検査)を行い、アカラシアachalasiaアカラシア(achalasia)achalasia(アカラシア)と食道体部 esophageal body 食道体部(esophageal body) esophageal body(食道体部) の収縮消失を除外することを求めている。これらを見逃して噴門形成術 fundoplication 噴門形成術(fundoplication) fundoplication(噴門形成術) を行うと、逆流ではなく通過障害 obstruction to passage 通過障害(obstruction to passage) obstruction to passage(通過障害) を悪化させる。1
バレット食道Barrett esophagusバレット食道(Barrett esophagus)Barrett esophagus(バレット食道)については、ACGの2022年バレット食道 Barrett esophagus バレット食道(Barrett esophagus) Barrett esophagus(バレット食道) ガイドラインが癌化予防を目的とした抗逆流手術 antireflux surgery 抗逆流手術(antireflux surgery) antireflux surgery(抗逆流手術) は行わないことを提案している(条件付き推奨、エビデンスの質は低い)。逆流の制御そのものを目的とする手術を禁じているのではなく、「発癌を抑える手段としては勧めない」という趣旨である。バレット食道Barrett esophagus バレット食道(Barrett esophagus)Barrett esophagus(バレット食道) の薬物治療としては少なくとも1日1回のPPI投与が提案され(条件付き推奨、エビデンスの質は非常に低い)、病理所見に応じた内視鏡サーベイランス endoscopic surveillance 内視鏡サーベイランス(endoscopic surveillance) endoscopic surveillance(内視鏡サーベイランス) を併せて行う。8
3.5 合併症
バレット食道Barrett esophagus バレット食道(Barrett esophagus)Barrett esophagus(バレット食道) (腸上皮化生intestinal metaplasia腸上皮化生(intestinal metaplasia)intestinal metaplasia(腸上皮化生))、逆流性食道炎reflux esophagitis逆流性食道炎(reflux esophagitis)reflux esophagitis(逆流性食道炎)、食道狭窄esophageal stricture食道狭窄(esophageal stricture)esophageal stricture(食道狭窄)、誤嚥性肺炎aspiration pneumonia誤嚥性肺炎(aspiration pneumonia)aspiration pneumonia(誤嚥性肺炎)、逆流性喉頭炎reflux laryngitis逆流性喉頭炎(reflux laryngitis)reflux laryngitis(逆流性喉頭炎)。
⚠️ バレット食道Barrett esophagus バレット食道(Barrett esophagus)Barrett esophagus(バレット食道) は腺癌の前駆病変 precursor lesion前駆病変(precursor lesion) precursor lesion(前駆病変)。詳細な病理と食道腺癌esophageal adenocarcinoma 食道腺癌(esophageal adenocarcinoma)esophageal adenocarcinoma(食道腺癌) (O/08)への進展は別項で扱う。
まとめ
- 食道裂孔ヘルニアhiatal hernia 食道裂孔ヘルニア(hiatal hernia)hiatal hernia(食道裂孔ヘルニア) は「裂孔の弛緩+腹圧上昇」で生じる解剖学的異常。I型が95%超を占め、II〜IV型をまとめて傍食道ヘルニア paraesophageal hernia 傍食道ヘルニア(paraesophageal hernia) paraesophageal hernia(傍食道ヘルニア) と呼ぶ。IV型を定義するのは胃の脱出量ではなく、胃以外の臓器(大網greater omentum大網(greater omentum)greater omentum(大網)・結腸・小腸など)がヘルニア嚢 hernial sac ヘルニア嚢(hernial sac) hernial sac(ヘルニア嚢) に入っていることである。4
- 無症候〜軽症の傍食道ヘルニア paraesophageal hernia 傍食道ヘルニア(paraesophageal hernia) paraesophageal hernia(傍食道ヘルニア) について、EAES 2023は一般には保存的管理 conservative management 保存的管理(conservative management) conservative management(保存的管理) より手術を提案する(条件付き推奨)が、虚弱な患者では手術より保存的管理 conservative management 保存的管理(conservative management) conservative management(保存的管理) を推奨する(強い推奨)。緊急手術に至る確率は年約1%である。2
- 扁平円柱上皮接合部squamocolumnar junction (Z-line) 扁平円柱上皮接合部(squamocolumnar junction (Z-line))squamocolumnar junction (Z-line)(扁平円柱上皮接合部) の偏位は内視鏡評価の参考所見であり、型分類は造影検査などと総合して判断する。9
- GERDは抗逆流バリア障害、一過性LES弛緩transient lower esophageal sphincter relaxation一過性LES弛緩(transient lower esophageal sphincter relaxation)transient lower esophageal sphincter relaxation(一過性LES弛緩)、食道クリアランスesophageal clearance 食道クリアランス(esophageal clearance)esophageal clearance(食道クリアランス) 低下、胃内圧intragastric pressure 胃内圧(intragastric pressure)intragastric pressure(胃内圧) 上昇などが関与する複合病態で、酸分泌過多hyperacidity 酸分泌過多(hyperacidity)hyperacidity(酸分泌過多) が主役ではない。
- 検査は目的で選ぶ。造影は形態と通過、内視鏡は粘膜病変、内圧検査は運動を評価し、GERDでは必要に応じて逆流モニタリングで診断を確かめる。すべての患者に全検査を必須としない。
- 治療の柱はプロトンポンプ阻害薬 proton pump inhibitor, PPI プロトンポンプ阻害薬(proton pump inhibitor, PPI) proton pump inhibitor, PPI(プロトンポンプ阻害薬) ((エス)オメプラゾール(es)omeprazole (エス)オメプラゾール((es)omeprazole)(es)omeprazole((エス)オメプラゾール) など)を中心とする内科的治療、無効例や合併症例には腹腔鏡下噴門形成術 laparoscopic fundoplication 腹腔鏡下噴門形成術(laparoscopic fundoplication) laparoscopic fundoplication(腹腔鏡下噴門形成術) (Nissen=360度)。
- 慢性GERDではバレット食道 Barrett esophagus バレット食道(Barrett esophagus) Barrett esophagus(バレット食道) や腺癌のリスクも問題になるが、全例がこの経路を進むわけではない。病理所見に応じた長期フォローが重要。
出典
- 1.ACG Clinical Guideline for the Diagnosis and Management of Gastroesophageal Reflux Disease(American College of Gastroenterology・2022)PMC8754510の著者最終稿全文を確認した。抗逆流手術について「客観的な逆流の証拠をもつ患者の長期治療の選択肢として、経験豊富な外科医が行う抗逆流手術を推奨する。とくにLA分類 grade C・Dの高度逆流性食道炎、大きな食道裂孔ヘルニア、残存する煩わしい逆流症状をもつ患者が最も恩恵を受ける」(強い推奨、エビデンスの質は中等度)。LA grade C・Dでは「PPIの無期限維持投与または抗逆流手術」を同一の推奨文で並べる(強い推奨、中等度)。抗逆流手術・内視鏡治療の前に高解像度食道内圧検査を行いアカラシアと無収縮を除外することも求めている。閲覧 2026-09-21
- 2.EAES Multidisciplinary Rapid Guideline: systematic review, meta-analysis, GRADE assessment and evidence-informed recommendations on the surgical management of paraesophageal hernias(European Association for Endoscopic Surgery・2023)Amsterdam UMC リポジトリ版(表紙が Publisher's PDF, also known as Version of record と明記)の全文を確認した。適用範囲は「胃の50%超が胸腔内へ脱出した中等度〜大型のII〜IV型傍食道ヘルニア」と明記されている。推奨は、無症候・軽症の傍食道ヘルニアに対し保存的管理より手術を提案する(条件付き推奨)、ただし虚弱な患者では手術より保存的管理を推奨する(強い推奨)、裂孔閉鎖は単純縫合よりメッシュを提案(条件付き)、待機手術では胃固定術より噴門形成術を提案(条件付き)、心肺機能が不安定で緊急修復を要する例では噴門形成術より胃固定術を提案(条件付き)。エビデンスの確実性は全転帰で非常に低く、パネルは本文書が無症候・軽症例を保存的に管理してきた外科医に診療の変更を求めるものだと述べている。緒言は、傍食道ヘルニア患者が急性症状を来し緊急手術を要する確率をプール解析で年約1%、診断年齢の中央値を65〜75歳としている。I〜IV型の定義そのものは本文書には無い。閲覧 2026-09-21
- 3.ACG Clinical Guidelines: Clinical Use of Esophageal Physiologic Testing(American College of Gastroenterology・2020)学会が公開する原著PDFの閉塞症状の評価節を確認した。内視鏡と生検で器質的・粘膜病変を評価し、機械的原因がない閉塞症状には高解像度食道内圧検査を用いる。造影検査やFLIPは補完的に位置づける。閲覧 2026-10-13
- 4.Guidelines for the Management of Hiatal Hernia(Society of American Gastrointestinal and Endoscopic Surgeons(SAGES)・2013)出版社版が購読制のため、SAGES 公式サイトの本文(Wayback の id_ 付きスナップショット)で全文を確認した。2013年4月に SAGES 理事会が承認した版で、筆頭著者は Kohn である。I型は滑脱型で胃食道接合部が横隔膜上へ移動し、胃は通常の長軸方向を保ち胃底部は胃食道接合部より下にとどまる。II型は純粋な傍食道ヘルニアで胃食道接合部は正常な解剖学的位置にとどまり胃底部の一部が食道の傍らから脱出する。III型はI型とII型の混合で胃食道接合部と胃底部がともに脱出し、胃底部は胃食道接合部より上に位置する。IV型は「胃以外の構造物、たとえば大網・結腸・小腸がヘルニア嚢内にあること」で特徴づけられる。食道裂孔ヘルニアの95%超がI型で、傍食道ヘルニアのうち90%超がIII型、最も少ないのがII型である。II〜IV型を一括して傍食道ヘルニアと呼び、胃食道接合部周囲の後外側の横隔食道付着が比較的保たれる点でI型と区別する。「巨大(giant)傍食道ヘルニア」の定義は一定せず、多くは胃の1/3〜1/2を超える部分が胸腔内にあるものを指す。閲覧 2026-09-21
- 5.Diagnosis and management of Barrett esophagus: European Society of Gastrointestinal Endoscopy (ESGE) Guideline(European Society of Gastrointestinal Endoscopy・2023)学会公開PDFの内視鏡評価節で、胃食道接合部と横隔膜の締め付け位置、Prague分類による化生範囲をそれぞれ記録し、胃粘膜ひだの口側端を起点に生検することを確認した。閲覧 2026-10-13
- 6.SAGES guidelines for the surgical treatment of hiatal hernias(SAGES・2024)学会公式サイトの推奨本文を確認した。II〜IV型の無症候例には手術と経過観察を直接比較する根拠が不足し、真に無症候かを評価したうえで共同意思決定を行う。検査で逆流・微小誤嚥などがなくリスクを理解する場合は経過観察も妥当。修復時の噴門形成は条件付き提案で、メッシュの一律使用には賛否の推奨を出していない。閲覧 2026-10-13
- 7.Laparoscopic antireflux surgery vs esomeprazole treatment for chronic GERD: the LOTUS randomized clinical trial(JAMA・2011)慢性GERD554例(欧州11か国)を対象とした5年間の無作為化試験(LOTUS試験)で、腹腔鏡下噴門形成術(LARS)とエソメプラゾール継続投与はいずれも5年時点で大半の患者が寛解を維持し(推定寛解率エソメプラゾール群92%、LARS群85%)、酸分泌抑制薬による内科治療と外科治療のいずれも現代的な逆流症管理として選択肢になることを確認した。閲覧 2026-08-26
- 8.Diagnosis and Management of Barrett's Esophagus: An Updated ACG Guideline(American College of Gastroenterology・2022)PMC10259184の著者最終稿全文を確認した。推奨16は「バレット食道患者において抗腫瘍的手段としての抗逆流手術は行わないことを提案する」(推奨の強さは条件付き、エビデンスの質は低い)であり、逆流制御を目的とする手術一般を否定してはいない。推奨14は「PPIに対する禁忌がないバレット食道患者に少なくとも1日1回のPPI投与を提案する」(条件付き、エビデンスの質は非常に低い)。閲覧 2026-09-21
- 9.Systematic review of the perioperative classification, diagnosis, description and repair of hiatus hernias in randomized controlled trials(Diseases of the Esophagus・2024)食道裂孔ヘルニアの診断・分類法には研究間のばらつきがあり、単一の内視鏡所見だけでなく複数の検査を総合して評価することを確認した。閲覧 2026-08-09